
Penile Curvature Surgery in Istanbul: 5 Key Techniques
Penile curvature surgery straightens an erect penis that bends enough to make sex difficult, painful or impossible. For congenital penile curvature, the bend a man has had since puberty or earlier, European urology guidelines state that surgery is the only effective treatment, usually a plication technique such as the Nesbit, 16-dot or Yachia procedure, which straightens the penis by shortening its longer side.
Source: EAU — Sexual and Reproductive Health Guidelines: Penile Curvature
- A slight bend is normal. A curve of more than 30° is generally considered clinically significant, but the real reason to operate is difficulty with intercourse or distress.
- Congenital curvature has no scar plaque, does not correct itself, and does not respond to pills, injections or devices. Surgery is the only treatment option.
- Plication techniques (Nesbit, 16-dot, Yachia) straighten the penis in most men in published series, but almost all men lose some length, usually around 1 cm or less.
- Expect swelling and bruising for several days and no sexual activity for about six weeks.
- Curvature that appears in adulthood, especially with a lump or pain, is usually Peyronie’s disease and follows a different treatment path.
Tell us about your curve and your history, and our urologist will tell you whether surgery makes sense for you.
- What is penile curvature surgery?
- How much penile curvature is normal?
- Who is a good candidate for penile curvature surgery?
- Penile curvature surgery options compared
- The procedure step by step
- Recovery timeline after penile curvature correction
- Risks and side effects
- Results and realistic expectations
- Treatment with Dr. Zülfü Sertkaya in Istanbul
- When to see a doctor
- FAQs about penile curvature surgery
What is penile curvature surgery?
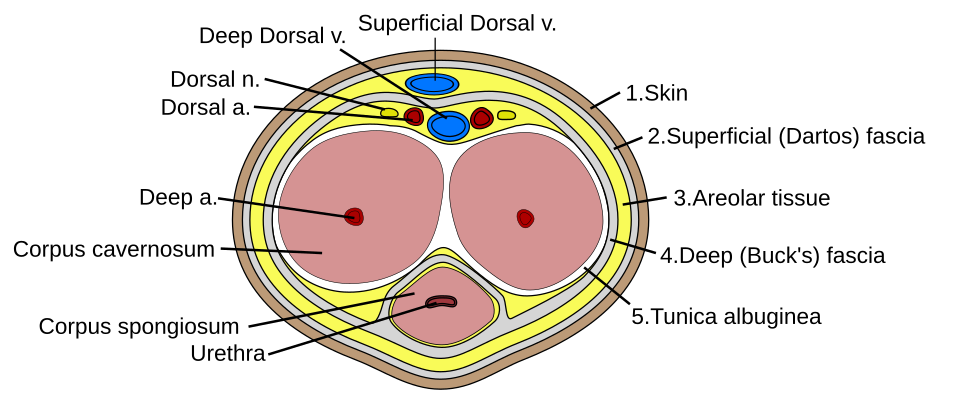
The two erectile chambers of the penis (the corpora cavernosa) are wrapped in a tough, elastic sheath called the tunica albuginea. In congenital penile curvature, this sheath develops unevenly, so one side stretches more than the other during an erection and the penis bends toward the shorter side. It is not caused by a problem with the urethra and is not linked to injury or disease.
Penile curvature correction is an operation on that sheath. The surgeon either shortens the longer side with stitches or small excisions (plication and corporoplasty techniques) or, much less often, lengthens the shorter side. For congenital curvature, shortening techniques are the standard approach.
Source: EAU — Sexual and Reproductive Health Guidelines: Penile Curvature; EAU — Paediatric Urology Guidelines: Congenital Penile Curvature
Congenital curvature vs Peyronie’s disease
Congenital curvature is present from birth but usually becomes obvious only after puberty, when erections become fuller. It is most often ventral (downward), less often lateral, and rarely dorsal (upward). It typically does not get worse over time, it will not correct itself with age, and there is no scar tissue in the penis.
Peyronie’s disease is different: it is acquired in adulthood, caused by a scar (plaque) in the tunica albuginea, and often comes with pain, a lump, narrowing or shortening. If your curve appeared recently, see our Peyronie’s disease treatment page, because the timing and options are not the same.
Source: Cleveland Clinic — Congenital Penile Curvature (Chordee); NHS — Peyronie’s disease
How much penile curvature is normal?
Penises vary a lot in shape, and a slight curve when erect is normal. Studies report some degree of curvature in 4–10% of males without hypospadias, while severe congenital curvature that needs surgery is uncommon (the EAU puts its incidence below 1%).
Specialists generally consider a curve greater than 30° clinically significant. Even so, many men with larger curves have no problems at all, so the decision is driven by function, not by a number on a protractor. Surgery becomes reasonable when the bend makes penetration difficult or painful, causes discomfort for a partner, or creates real distress about appearance.
That distress matters: in a survey cited by the EAU, men with untreated ventral curvature reported more dissatisfaction with appearance, more difficulty with intercourse and more psychological problems than men without it.
Source: EAU — Paediatric Urology Guidelines: Congenital Penile Curvature; PMC — Abnormalities of Penile Curvature: Chordee and Penile Torsion; NHS — Peyronie’s disease
Who is a good candidate for penile curvature surgery?
The typical candidate for penile curvature surgery is an adult man whose congenital bend interferes with intercourse or causes significant bother, and whose erections are otherwise good. Guidelines advise waiting until after puberty, because the penis is still growing before then; once growth is complete, the operation is a definitive, one-time correction for most men.
- Good erections and a curve under about 60°: plication is usually the first choice.
- Very severe or complex curves: lengthening (grafting) techniques may be considered, at a higher risk to erections and sensation.
- Curvature plus erectile dysfunction that does not respond to tablets: a penile prosthesis can treat both problems in one operation.
Source: EAU — Sexual and Reproductive Health Guidelines: Penile Curvature; BAUS — Penile straightening by plication or grafting (patient leaflet)
How the curvature is assessed
A medical and sexual history usually explains the cause. The EAU calls examination and photographic documentation of the erect penis mandatory, ideally after an intracavernosal injection, a small injection of a vasoactive drug into the side of the penis that produces a full erection in the clinic. Photos taken at home from several angles (from above and from the side) are also helpful.
The surgeon also records stretched penile length, the direction and angle of the bend, any narrowing or rotation, and the quality of your erections, because these decide which technique fits. The exact angle is confirmed again during surgery with an artificial erection test.
Source: EAU — Sexual and Reproductive Health Guidelines: Penile Curvature; EAU — Paediatric Urology Guidelines: Congenital Penile Curvature
Why non-surgical options do not straighten a congenital curve
Collagenase injections, traction devices and vacuum devices are discussed for Peyronie’s disease, where the target is a scar plaque. A congenital curve has no plaque; the sheath itself is simply longer on one side. That is why the EAU states that surgery is the only treatment option for congenital penile curvature, and no tablet, cream, injection or stretching programme has been shown to correct it. Be cautious of clinics that sell such treatments for a curve you were born with.
Source: BAUS — Penile straightening by plication or grafting (patient leaflet); EAU — Sexual and Reproductive Health Guidelines: Penile Curvature; Cleveland Clinic — Congenital Penile Curvature (Chordee)
Penile curvature surgery options compared
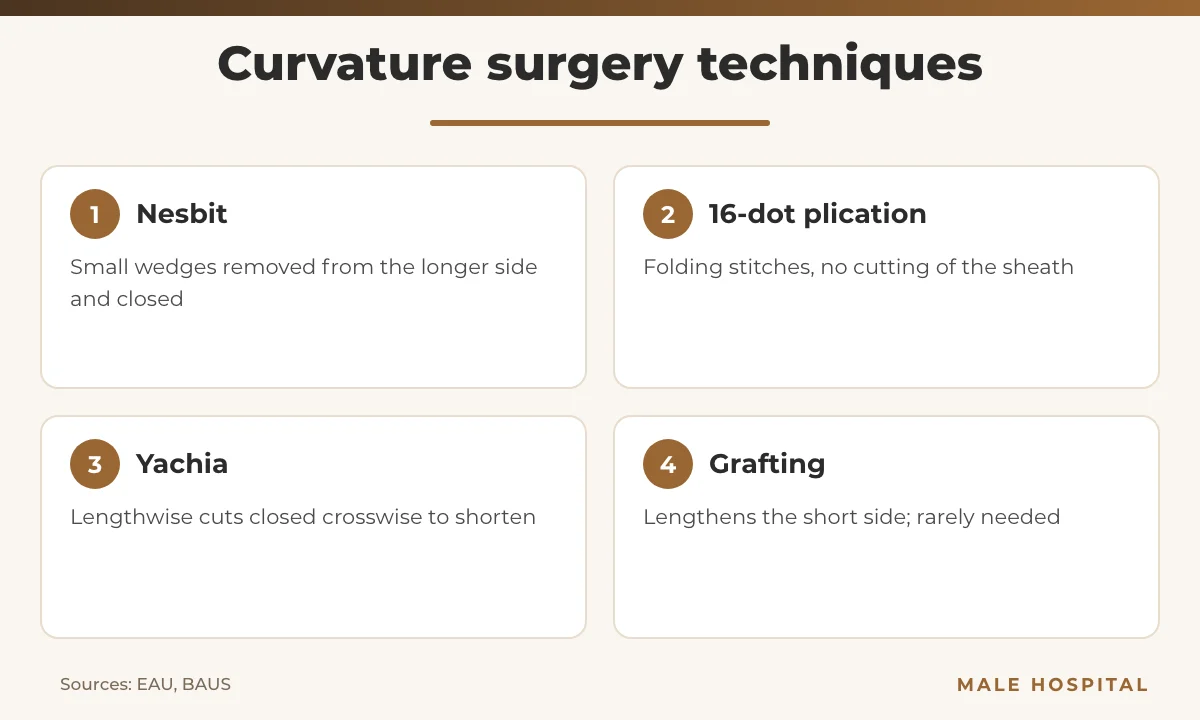
Several shortening techniques exist, and the EAU notes that no direct comparative studies allow one to be recommended over the others. Its strong recommendation is to use the Nesbit/Yachia procedure or other plication techniques, with or without dissecting the neurovascular bundle (the nerves and vessels on top of the penis).
Nesbit procedure
The classic Nesbit operation removes small wedges of tunica albuginea on the longer side and closes the gaps, which pulls that side shorter. A modified Nesbit removes only a very superficial layer of the sheath.
Plication techniques: 16-dot and others
Plication folds the sheath with permanent stitches without cutting it. Lue’s 16-dot technique uses a set pattern of plication stitches placed on the side opposite the bend. Some surgeons perform plication through a small 2–3 cm incision on the shaft instead of fully “degloving” the penile skin from just behind the head.
Yachia technique
The Yachia procedure makes short lengthwise cuts in the sheath on the longer side and closes them crosswise (the Heineke–Mikulicz principle), which shortens that side.
Corporoplasty and derotation
Corporoplasty is a broad term for reshaping the erectile bodies. Corporal body derotation has been reported to cause minimal narrowing and shortening. In rare cases that need the short side lengthened, surgeons use corporotomies or corporoplasty with a graft.
Source: EAU — Sexual and Reproductive Health Guidelines: Penile Curvature; EAU — Paediatric Urology Guidelines: Congenital Penile Curvature; PMC — Plication for Correction of Congenital Penile Curvature: With or Without Degloving?
| Technique | How it works | Straightening* | Reduced sensation* | Main trade-off |
|---|---|---|---|---|
| Nesbit | Wedges of sheath removed and closed | 88.5% | 11.8% | Shortening; sensation changes |
| Modified Nesbit | Superficial excision of sheath | 97.1% | 7.7% | Length loss reported often |
| 16-dot plication | Folding stitches, no cutting | 96.9% | 8.2% | Suture-related problems, palpable knots |
| Yachia | Lengthwise cuts closed crosswise | 95.5% | 1% | Shortening |
| Grafting (lengthening) | Short side cut and patched | — | Higher | More risk to erections; rarely needed in congenital cases |
*Weighted averages from mostly retrospective, non-comparable studies summarised in the EAU guideline’s Peyronie’s disease section; congenital surgery follows the same principles, but figures are not directly transferable. Source: EAU — Sexual and Reproductive Health Guidelines: Penile Curvature; BAUS — Penile straightening by plication or grafting (patient leaflet)
What head-to-head studies show
A Turkish multicentre study of 387 men (260 with congenital curvature) compared Lue’s 16-dot plication with a modified Nesbit. Complete straightening was similar (87.6% vs 89.7%), but sensory loss and new erectile dysfunction were more common after the modified Nesbit, while suture-related complications were more common after 16-dot plication. Men with congenital curvature lost less length and had less new erectile dysfunction than men with Peyronie’s disease.
A smaller 2025 study of 68 men comparing Yachia, Nesbit and 16-dot plication found no significant differences in shortening, sensation loss or recurrence; painful erections were more frequent after Nesbit. The practical message: the surgeon’s experience and your anatomy matter more than the name of the technique.
Source: PubMed — Comparison of 2 Penile Plication Techniques: Lessons Learned From 387 Patients (Urology, 2019); Canadian Urological Association Journal — Comparative outcomes of three tunical shortening techniques (2025)
The procedure step by step
- Consent and anaesthesia: the surgeon reviews your history and the planned technique; the operation is done under general or spinal anaesthesia, often with a local nerve block for pain relief afterward.
- Artificial erection: on the operating table an erection is induced to confirm the direction and angle of the curve.
- Access: the skin is either rolled back through a cut just behind the head of the penis (degloving) or opened through a short incision on the shaft.
- Correction: the longer side is shortened with plication stitches, Nesbit excisions or Yachia incisions, and the erection test is repeated until the penis is functionally straight.
- Closing: the skin is closed with dissolvable stitches. If the foreskin is tight, a circumcision may be done at the same time.
- Dressing and catheter: a firm dressing limits bruising and swelling, and a urinary catheter may be placed for a short time.
BAUS reports that plication takes about one to two hours and that patients in UK practice are usually discharged 24–48 hours later.
Source: BAUS — Penile straightening by plication or grafting (patient leaflet); PMC — Plication for Correction of Congenital Penile Curvature: With or Without Degloving?
Recovery timeline after penile curvature correction

| When | What to expect |
|---|---|
| Day of surgery | Operation of about 1–2 hours; firm dressing; possibly a catheter |
| 24–72 hours | Dressing usually removed; discharge typically within 24–48 hours |
| First days | Swelling and bruising of the penis and scrotum; normal night or morning erections may occur |
| 2–3 weeks | Dissolvable stitches usually disappear (occasionally later) |
| 6 weeks | No intercourse or masturbation until about this point, then resume as advised |
| After 6 weeks | Some surgeons advise a vacuum device for gentle penile stretching |
Ask your surgeon when you can return to work and travel, since this depends on the technique and your job. Stopping smoking before surgery lowers the risk of complications.
Source: BAUS — Penile straightening by plication or grafting (patient leaflet)
Risks and side effects
Every shortening operation trades a little length for a straight penis, and you should hear this clearly before surgery. BAUS lists the following typical after-effects of plication:
- Almost all patients: some penile shortening; a small residual curve under 20° that should still allow sex; temporary swelling and bruising.
- About 1 in 4: circumcision needed as part of the procedure.
- About 1 in 20: erectile dysfunction; temporary or permanent numbness from nerve injury.
- Between 1 in 10 and 1 in 50: recurrence of curvature; dissatisfaction with the result; significant bleeding or infection.
The EAU adds palpable knots or stitches under the skin, delayed orgasm and the need to understand that the goal is a “functionally straight” penis, not a perfectly straight one. Painful erections and suture-related problems have also been reported in comparative studies.
Source: BAUS — Penile straightening by plication or grafting (patient leaflet); EAU — Sexual and Reproductive Health Guidelines: Penile Curvature
Length loss after penile curvature surgery
In mixed series, the EAU reports shortening of 1–1.5 cm in 22–69% of patients. In congenital cases specifically, the loss is often smaller: one study found up to 1 cm of length loss in 6% of patients with curves over 30°, and a 38-man study of congenital curvature found an average change in stretched length of only 0.1 cm with small-incision plication versus 1.1 cm with degloving plication.
Source: EAU — Sexual and Reproductive Health Guidelines: Penile Curvature; EAU — Paediatric Urology Guidelines: Congenital Penile Curvature; PMC — Plication for Correction of Congenital Penile Curvature: With or Without Degloving?
Sensation changes and recurrence
Reduced sensitivity of the glans can happen when the nerves on top of the penis are handled; it is often temporary. In the small-incision plication series above, no man reported reduced glans sensation, while earlier degloving studies reported it in up to 37%. Recurrence and numbness are uncommon overall, at roughly 10% according to the EAU.
Source: PMC — Plication for Correction of Congenital Penile Curvature: With or Without Degloving?; EAU — Paediatric Urology Guidelines: Congenital Penile Curvature; EAU — Sexual and Reproductive Health Guidelines: Penile Curvature
Results and realistic expectations
The largest systematic review of adult congenital curvature surgery (55 studies, 2,956 men) found reported straightening success rates of 75–100 percent for plication and 73–100 percent for corporoplasty, with relatively low complication rates. The authors warn that most studies are low-quality and report outcomes differently, so no technique can be declared superior. The EAU paediatric guideline gives an overall correction rate of 90 to 100 percent in most series, with equally high satisfaction.
Realistic goals are a penis that is straight enough for comfortable intercourse, a small loss of length, possible palpable stitches, and a low but real chance of numbness, erection problems or recurrence. No straightening operation can make a penis look exactly as you imagine, and none adds length. If your main concern is size rather than shape, read about penis enlargement options separately.
Source: PubMed — Surgical Correction of Adult Congenital Penile Curvature: A Systematic Review (J Sex Med, 2022); EAU — Paediatric Urology Guidelines: Congenital Penile Curvature; BAUS — Penile straightening by plication or grafting (patient leaflet)
Treatment with Dr. Zülfü Sertkaya in Istanbul
Your assessment and penile curvature surgery are planned by Assoc. Prof. Dr. Zülfü Sertkaya, a urologist and andrologist in Istanbul. He has been a urology specialist since 2014, is a Fellow of the European Board of Urology (FEBU, 2017) and became Associate Professor of Urology in 2020. His clinical focus includes Peyronie’s disease and penile prosthesis surgery, and he is a member of the European Association of Urology (EAU), the European Society for Sexual Medicine (ESSM) and the International Society for Sexual Medicine (ISSM). He founded and works at Andro Expertise Men’s Health and Aesthetic Clinic in Zeytinburnu, Istanbul.
For patients travelling to Istanbul we arrange reception and transport, translation, trip planning, hotel accommodation, the medical consultation and aftercare follow-up. Pricing is given after a free assessment, because it depends on your curve and the technique chosen.
How to start
Send us a confidential WhatsApp message with your age, how long you have had the curve, its direction, whether it causes problems with sex, and any medical conditions or previous surgery. The doctor reviews this and suggests a personalised plan, including whether surgery is appropriate at all. If erections are also weak, he may discuss erectile dysfunction treatment first.
When to see a doctor
See a urologist if your penis curves enough to make sex difficult or painful, or if the curve worries you. Seek prompt assessment if:
- a new bend appears in adulthood, especially with a hard lump, narrowing or shortening (possible Peyronie’s disease);
- erections are painful or you have new erection problems;
- after surgery you notice signs of significant bleeding or infection; contact your surgeon promptly.
Source: NHS — Peyronie’s disease; BAUS — Penile straightening by plication or grafting (patient leaflet)
Get an honest, confidential opinion on whether your curve needs surgery.
FAQs about penile curvature surgery
What degree of penile curvature needs surgery?
There is no single cut-off. Curves above 30° are generally considered clinically significant, yet many men with larger bends have normal sex lives. Surgery is advised when the curve makes penetration difficult or painful or causes real distress. A slight curve on its own is normal and does not need treatment.
Source: EAU — Paediatric Urology Guidelines: Congenital Penile Curvature
Can congenital penile curvature be fixed without surgery?
No proven non-surgical treatment exists. Congenital curvature comes from an uneven sheath, not a scar, so injections and traction designed for Peyronie’s plaques do not address it. The European Association of Urology states that surgery is the only treatment option, and the curve does not straighten by itself with age.
Source: EAU — Sexual and Reproductive Health Guidelines: Penile Curvature; Cleveland Clinic — Congenital Penile Curvature (Chordee)
Will penile curvature surgery make my penis shorter?
Some shortening is expected with any plication or Nesbit-type operation, because the longer side is brought back to match the shorter side. In congenital cases the loss is usually small, often under 1 cm, and studies show congenital patients lose less length than men with Peyronie’s disease. Your surgeon should measure stretched length before surgery.
Which is better, Nesbit or plication?
Neither has been proven better. Large reviews report high straightening rates for both. A 387-patient study found similar straightening, more sensory loss and new erection problems after modified Nesbit, and more suture-related problems after 16-dot plication. The best choice depends on your curve and your surgeon’s experience.
How long until I can have sex after the operation?
BAUS advises avoiding all sexual activity, including masturbation, for six weeks after penile straightening. Normal erections in the first days after surgery are expected. Your surgeon may also recommend a vacuum device afterward for gentle stretching. Follow the specific instructions you are given at discharge.
Source: BAUS — Penile straightening by plication or grafting (patient leaflet)
Will I lose sensation after penile curvature surgery?
Most men do not. Reduced glans sensitivity is reported in a minority, about 1 in 20 in BAUS figures for plication, and is often temporary. In one small congenital study, plication through a short shaft incision caused no reported loss of glans sensation.
Source: BAUS — Penile straightening by plication or grafting (patient leaflet); PMC — Plication for Correction of Congenital Penile Curvature: With or Without Degloving?
Can the curve come back after surgery?
Yes, but not often. BAUS estimates recurrence at between 1 in 10 and 1 in 50 patients, and the EAU describes recurrence as uncommon. If a recurrent curve causes problems, a repeat plication is possible, as happened in one man in a 38-patient congenital series.
Source: BAUS — Penile straightening by plication or grafting (patient leaflet); PMC — Plication for Correction of Congenital Penile Curvature: With or Without Degloving?
Is penile curvature surgery done under general anaesthesia?
Usually it is done under general or spinal anaesthesia, often combined with a local nerve block so the penis stays comfortable after you wake up. The operation itself typically takes one to two hours for plication, and most patients go home within one to two days.
Source: BAUS — Penile straightening by plication or grafting (patient leaflet)
Should a teenager have surgery for congenital curvature?
Guidelines advise waiting until penile growth is complete after puberty, and it is reasonable to postpone surgery until the young man can make the decision himself. Correction in adulthood is appropriate when the curve causes real functional problems during intercourse.
Source: EAU — Paediatric Urology Guidelines: Congenital Penile Curvature; EAU — Sexual and Reproductive Health Guidelines: Penile Curvature
Medically reviewed by Assoc. Prof. Dr. Zülfü Sertkaya, urologist and andrologist (FEBU), Istanbul. Last reviewed: October 2026.
This article is for general information and does not replace an individual consultation with a qualified doctor.
- EAU — Sexual and Reproductive Health Guidelines: Penile Curvature
- EAU — Paediatric Urology Guidelines: Congenital Penile Curvature
- BAUS — Penile straightening by plication or grafting (patient leaflet)
- Cleveland Clinic — Congenital Penile Curvature (Chordee)
- NHS — Peyronie's disease
- PubMed (J Sex Med, 2022) — Surgical Correction of Adult Congenital Penile Curvature: A Systematic Review
- PubMed (Urology, 2019) — Comparison of Patient's Satisfaction and Long-term Results of 2 Penile Plication Techniques: Lessons Learned From 387 Patients With Penile Curvature
- PMC (Sex Med, 2021) — Plication for Correction of Congenital Penile Curvature: With or Without Degloving?
- PMC (Scientific World Journal, 2011) — Abnormalities of Penile Curvature: Chordee and Penile Torsion
- Canadian Urological Association Journal (2025) — Comparative outcomes and patient satisfaction rates of three tunical shortening techniques used for the correction of penile curvatures