

Delayed ejaculation is a persistent, bothersome difficulty or inability to reach orgasm and ejaculate, even with enough sexual stimulation and a normal erection. Common causes include antidepressants such as SSRIs, diabetes and other forms of nerve damage, surgery, thyroid problems and psychological or relationship factors. No drug is approved for it, so treatment targets the cause: adjusting medicines, sex therapy, treating hormone problems and, for some men, penile vibratory stimulation.
Source: EAU Guidelines — Disorders of ejaculation; AUA/SMSNA — Disorders of Ejaculation Guideline
- Delayed ejaculation (DE) is the least studied male sexual problem. Estimates suggest about 1% of men have the lifelong form and about 4% the acquired form.
- There is no strict time cut-off. Distress, frequency and a change from your usual pattern matter more than a stopwatch.
- Medicines (especially SSRI antidepressants), diabetes, nerve injury or surgery, low thyroid hormone and psychological factors are the main causes.
- EAU and AUA guidelines agree there is not enough evidence for any drug to be a proven treatment; all drugs used are off-label.
- Treatment is cause-specific: change the culprit medicine, treat the underlying disease, use sex therapy, and use vibratory stimulation or sperm retrieval when fertility is the goal.
- What is delayed ejaculation?
- How long is too long? Timing and types
- What causes delayed ejaculation?
- Similar conditions: anejaculation, anorgasmia and retrograde ejaculation
- How doctors make the diagnosis
- Delayed ejaculation treatment: what the guidelines say
- Fertility options when ejaculation fails
- When to see a doctor
- FAQs about delayed ejaculation
What is delayed ejaculation?
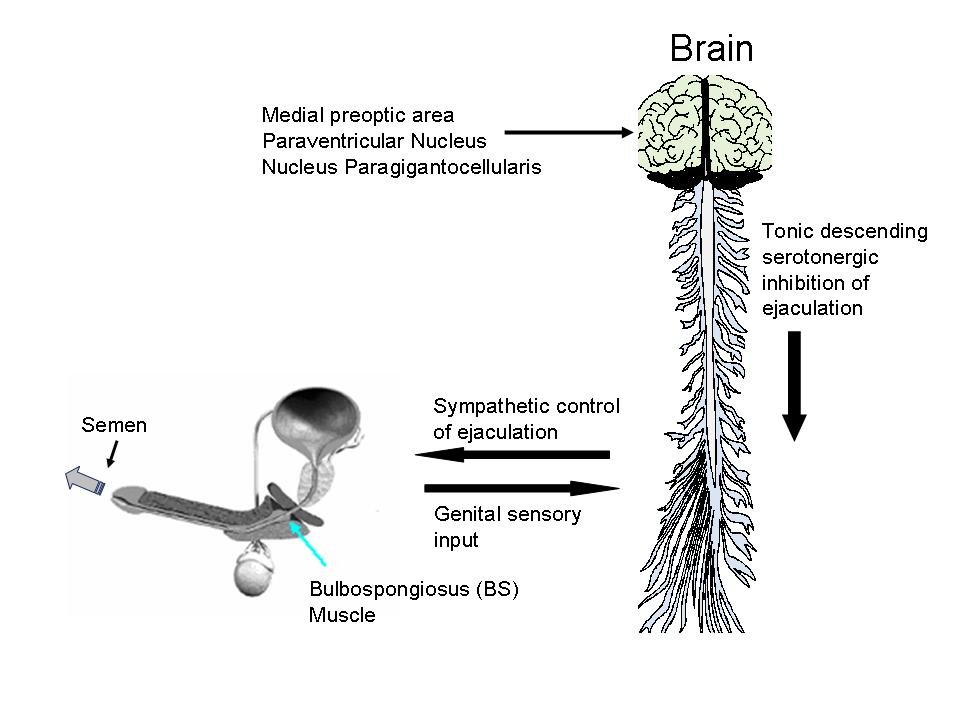
Ejaculation is a reflex controlled by the brain, the spinal cord and the nerves of the pelvis. Touch and arousal send signals up the spinal cord, and the sympathetic nervous system then moves semen into the urethra while the pelvic floor muscles push it out. Serotonin pathways in the brain act as a brake on this reflex. When any part of the circuit is slowed by a medicine, a disease, an injury or the mind, climax can take much longer or not happen at all.
The American Psychiatric Association definition used by the European Association of Urology (EAU) describes delayed ejaculation as a marked delay, infrequency or absence of ejaculation on at least 75% of occasions, lasting at least six months and causing personal distress. The American Urological Association (AUA) and the Sexual Medicine Society of North America (SMSNA) define it more simply as a consistent, bothersome inability to achieve ejaculation, either lifelong or acquired.
It is sometimes called male orgasmic disorder, retarded ejaculation or inhibited ejaculation. It is the opposite end of the timing spectrum from premature ejaculation, and it is much less common and less studied. The AUA guideline calls it arguably the least studied, least reported and least understood male sexual dysfunction.
Source: EAU Guidelines — Disorders of ejaculation; AUA/SMSNA — Disorders of Ejaculation Guideline
How common is it?
Good numbers are scarce. The EAU guideline estimates lifelong delayed ejaculation at about 1% of men and acquired DE at about 4%, while noting the evidence is limited. Community studies give a wide range: a Danish study of 1,181 men found 4.6%, and an Argentinian survey of 2,456 men found 14.1%. About three quarters of cases are acquired after a period of normal function.
Source: PMC — Jiann. The office management of ejaculatory disorders (Transl Androl Urol 2016); EAU Guidelines — Disorders of ejaculation
How long is too long? Timing and types
Most men ejaculate a few minutes after penetration. The AUA guideline puts the median time in Western countries at about 5–6 minutes, and the International Society for Sexual Medicine (ISSM) quotes a median of 5.4 minutes. ISSM uses about 22 minutes or more of stimulation as a rough benchmark, which sits near the 98th percentile. The AUA notes that times beyond 25–30 minutes with distress, or stopping sex because of fatigue or a sense of futility, are usually enough for the diagnosis.
These numbers are guides, not rules. A man who takes 30 minutes and is happy with it does not have a disorder. Another man who suddenly takes far longer than he used to, and feels frustrated, may have delayed ejaculation even at 15 minutes.
Source: ISSM — Q&A on ejaculation time; AUA/SMSNA — Disorders of Ejaculation Guideline
Lifelong, acquired, generalized or situational
Doctors describe delayed ejaculation along two lines. Lifelong DE has been present since the first sexual experiences, while acquired DE starts after a period of normal ejaculation, often pointing to a new medicine, illness or life event. Generalized DE happens in all situations; situational DE happens only in some, for example with a partner but not during masturbation. An ISSM-reported survey of 2,679 men found that men with DE reported longer average and minimum times to ejaculate with a partner, fewer sexual episodes ending in orgasm, less orgasmic pleasure and more distress.
Source: ISSM — Survey of men with DE symptoms; ISSM — Q&A on ejaculation time
What causes delayed ejaculation?
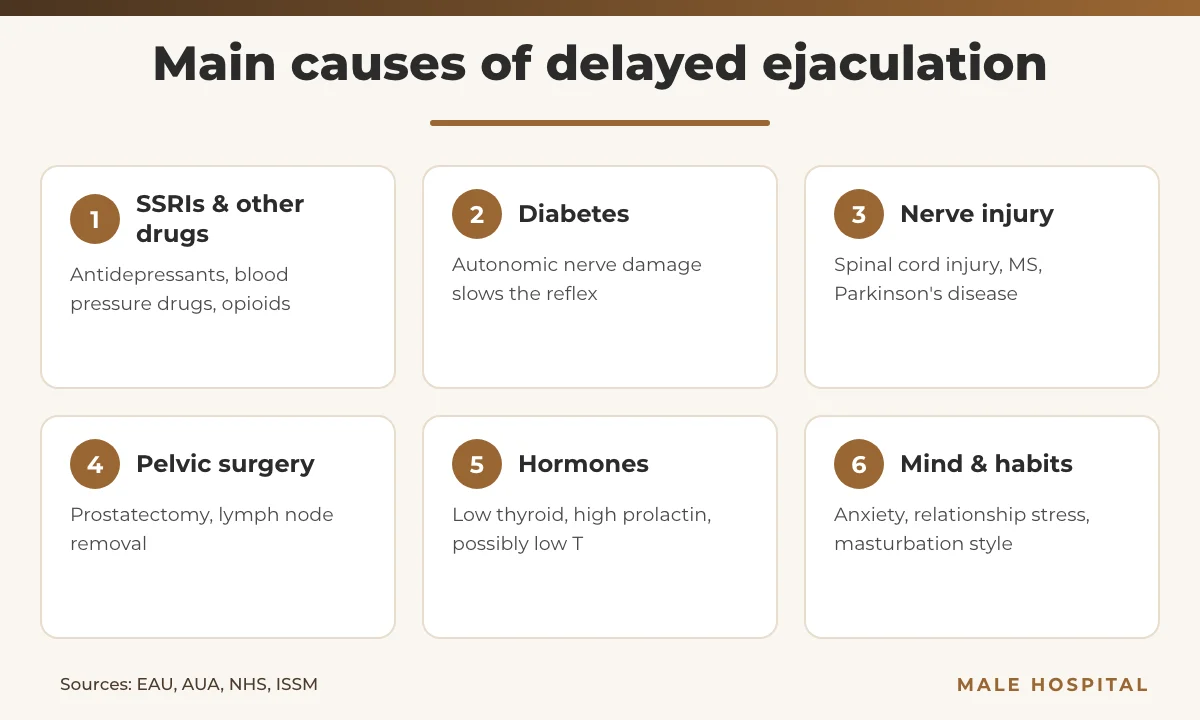
Experts agree that delayed ejaculation is usually multifactorial, with organic (physical) and psychological factors often working together. The main groups are below.
Medicines, especially SSRIs
Medication is one of the most common and most reversible causes of delayed ejaculation. Selective serotonin reuptake inhibitors (SSRIs) such as sertraline, fluoxetine or paroxetine raise serotonin, which strengthens the brain’s natural brake on ejaculation. This effect is so reliable that serotonin-acting drugs, including dapoxetine, are used to treat premature ejaculation. The EAU also lists antihypertensives, thiazide diuretics, alpha-blockers, antipsychotics, antiandrogens, opioids and alcohol. The NHS adds beta-blockers, and Cleveland Clinic notes heavy alcohol or recreational drug use.
Source: EAU Guidelines — Disorders of ejaculation; NHS — Ejaculation problems
Diabetes and nerve damage
Ejaculation depends on healthy autonomic nerves. Diabetic autonomic neuropathy can slow or block the reflex, and ISSM notes that poorly controlled diabetes can contribute to DE. Diabetes also harms erections; our guide to erectile dysfunction and diabetes covers that side. Other neurological causes include spinal cord injury, multiple sclerosis, Parkinson’s disease and stroke.
Source: EAU Guidelines — Disorders of ejaculation; ISSM — Q&A on ejaculation time
Surgery and pelvic injury
Operations near the nerves that control ejaculation can damage them. The EAU lists radical prostatectomy and lymph node removal (lymphadenectomy), and the NHS mentions bladder or prostate surgery. The AUA advises doctors to ask about pelvic or nervous system trauma, including injury caused by surgery.
Source: NHS — Ejaculation problems; AUA/SMSNA — Disorders of Ejaculation Guideline
Hormones: thyroid, prolactin and low testosterone
An underactive thyroid (hypothyroidism) is a recognized cause of delayed ejaculation. In a small multicenter study, 64.3% of 14 men with hypothyroidism had DE; after thyroid treatment, DE improved in half of them and the average time to ejaculate fell from about 22 to 7 minutes. High prolactin (hyperprolactinemia) is also listed by the EAU.
The role of low testosterone is less clear. Older studies linked it to DE, but the EAU states that newer studies have not confirmed an association with ejaculation time. A 16-week randomized trial in 76 men with low testosterone and ejaculatory problems found that testosterone gel did not improve symptoms more than placebo. Still, the AUA says doctors may offer treatment to normalize testosterone in men with DE (expert opinion), and ISSM notes it may help when levels are truly low. If you suspect a hormone problem, read about low testosterone symptoms and get a proper blood test.
Sources: PubMed — Carani et al. Sexual symptoms in hypo- and hyperthyroid men (J Clin Endocrinol Metab 2005); PubMed — Paduch et al. Testosterone replacement in androgen-deficient men with ejaculatory dysfunction: RCT (2015)
Psychological and relationship factors
Anxiety, depression, stress, relationship conflict, performance anxiety, fear of pregnancy or infection, and sexual guilt from cultural or religious upbringing can all hold back climax. Masturbation style matters too: the AUA notes that idiosyncratic or very forceful masturbation habits are linked to difficulty climaxing during partnered sex, because a partner cannot reproduce that specific pressure or speed. Ageing, with natural changes in hormones and penile sensitivity, adds to the picture.
Source: Cleveland Clinic — DE overview; AUA/SMSNA — Disorders of Ejaculation Guideline
Similar conditions: anejaculation, anorgasmia and retrograde ejaculation
Several conditions look similar but are managed differently, so the exact label matters.
| Condition | What happens | Typical causes |
|---|---|---|
| Delayed ejaculation | Climax takes a very long time or happens only sometimes | Medicines, nerve damage, thyroid problems, psychological factors |
| Anejaculation | No ejaculation at all, forward or backward | Nervous system damage (spinal cord injury, lymph node surgery, neuropathy) or drugs |
| Anorgasmia | No feeling of orgasm | Mostly psychological; the EAU attributes about 90% of cases to psychological factors |
| Retrograde ejaculation | Orgasm happens but semen flows back into the bladder | Prostate or bladder neck surgery, alpha-blockers, diabetes and other nerve damage |
Retrograde ejaculation matters mainly for fertility, and the EAU describes recovering sperm from urine passed after orgasm. If early climax is your problem instead, see our premature ejaculation treatment page.
Source: EAU Guidelines — Disorders of ejaculation; PubMed — Abdel-Hamid & Ali (World J Mens Health 2018)
How doctors make the diagnosis
There is no single gold-standard test. The history is the key to the diagnosis, and the AUA classes a medical, relationship and sexual history plus a focused physical exam as a clinical principle.
Questions your doctor will ask
- Has it always been this way, or did it start after a new medicine, illness, surgery or life event?
- Can you ejaculate during masturbation, with a partner, or neither? Do you wake with wet dreams?
- Which medicines, alcohol or drugs do you use, and do you also have erection, desire or bladder problems?
- How do you and your partner feel about it, and are you trying to conceive?
Examination and tests
The exam looks for signs of low testosterone, metabolic disease or past injury, and includes a genital exam, anal sphincter tone and the bulbocavernosus reflex, a quick check of the pelvic nerves. The AUA recommends measuring serum testosterone, with further tests only as findings suggest (conditional recommendation, evidence grade C). Common blood tests include glucose for diabetes, and testosterone, prolactin and thyroid-stimulating hormone (TSH). The EAU adds that loss of penile sensitivity needs further investigation. A urinalysis may also be done, and a fertility workup with semen analysis is added when conception is a goal.
Sources: AUA/SMSNA — Disorders of Ejaculation Guideline; PMC — Jiann. The office management of ejaculatory disorders; Cleveland Clinic — DE overview
Delayed ejaculation treatment: what the guidelines say
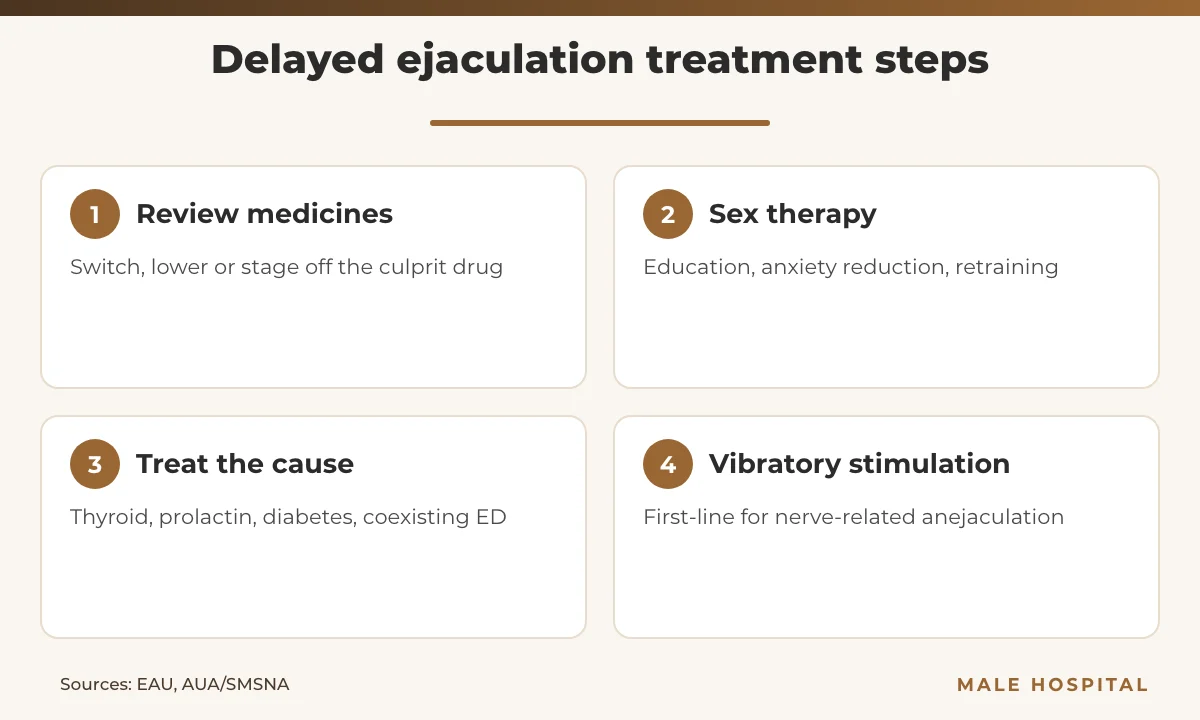
Both major guidelines are frank about the evidence. The EAU states there is not enough evidence to support a definitive treatment for delayed ejaculation. The AUA/SMSNA guideline notes that none of the drugs used has US Food and Drug Administration (FDA) approval for DE, so every medicine is off-label, and it recommends shared decision-making with the partner involved where possible.
Source: EAU Guidelines — Disorders of ejaculation; PubMed — Shindel et al. Disorders of Ejaculation: An AUA/SMSNA Guideline (J Urol 2022)
1. Review and change the culprit medicine
The AUA advises clinicians to suggest replacing the drug, adjusting the dose or stopping it in stages when a medicine is to blame (clinical principle). Never stop an antidepressant on your own; discuss it with the prescriber. A Cochrane review of 23 trials found some support for adding bupropion 150 mg twice daily for antidepressant-related sexual problems, while most other add-on drugs did not beat placebo. The NHS lists amantadine, bupropion or yohimbine as options to counter SSRI effects.
Source: PubMed — Taylor et al. Strategies for managing sexual dysfunction induced by antidepressant medication (Cochrane 2013); NHS — Ejaculation problems
2. Sex therapy and behavioral changes
The AUA suggests referring men with lifelong or acquired DE to a mental health professional with expertise in sexual health, and notes that changing sexual positions or practices to increase arousal may help. The EAU describes psychotherapy that includes sexual education, anxiety reduction and retraining of masturbation habits. A 2024 randomized trial cited by the EAU found that sex therapy combined with vacuum negative-pressure massage worked better than sex therapy or instruction alone.
Source: AUA/SMSNA — Disorders of Ejaculation Guideline; EAU Guidelines — Disorders of ejaculation
3. Treat the underlying condition
Better diabetes control, thyroid hormone replacement for hypothyroidism and treatment of high prolactin address the cause directly. The AUA advises treating any coexisting erectile dysfunction according to its ED guideline, since a weak erection makes climax harder.
Source: ISSM — Q&A on ejaculation time; AUA/SMSNA — Disorders of Ejaculation Guideline
4. Off-label medicines
Cabergoline, bupropion, buspirone, amantadine, cyproheptadine, oxytocin, yohimbine, alpha-1 agonists, apomorphine and testosterone have all been tried. The EAU states that none has proven efficacy or superiority, and a provider survey reported overall success of about 40%. The AUA advises counseling men that there is insufficient evidence to judge the risks and benefits of oral drugs. A review of the drug literature concluded that evidence is still limited to small trials, case series and case reports.
Cabergoline gets the most attention. In a retrospective pilot study of 131 men with delayed orgasm or anorgasmia, 66.4% reported subjective improvement on 0.5 mg twice weekly, but there was no control group and the authors call for randomized trials.
Sources: PubMed — Abdel-Hamid et al. Drug treatment review (2016); PubMed — Hollander et al. Cabergoline in male orgasmic disorder (Sex Med 2016)
5. Penile vibratory stimulation
Penile vibratory stimulation (PVS) uses a medical vibrator applied to the penis to trigger the ejaculation reflex. ISSM calls it an easy and accessible first option for delayed ejaculation. For anejaculation after spinal cord injury, lymph node surgery or neuropathy, the EAU names PVS as first-line therapy; adding midodrine led to ejaculation in almost 65% of men with spinal cord injury. The AUA adds that no data show a benefit from invasive non-drug procedures for DE.
Source: EAU Guidelines — Disorders of ejaculation; ISSM — Q&A on ejaculation time
Fertility options when ejaculation fails
For couples trying to conceive, delayed ejaculation and anejaculation can be the main barrier. When PVS fails, the EAU says electroejaculation, which uses a probe to stimulate the nerves electrically, can be the therapy of choice, and surgical sperm retrieval is used if that fails. A review in the World Journal of Men’s Health also lists collecting nocturnal emissions, prostatic massage, and sperm aspiration from the vas deferens or epididymis, and testicular sperm extraction. Sperm obtained this way can be used for assisted reproduction.
Source: EAU Guidelines — Disorders of ejaculation; PubMed — Abdel-Hamid & Ali (World J Mens Health 2018)
When to see a doctor
Cleveland Clinic advises seeing a provider when you first notice trouble ejaculating, especially if it frustrates you or your partner. Book an appointment sooner if you notice:
- Delayed or absent ejaculation that began after starting a new medicine
- Numbness in the penis, groin or legs, new weakness, or bladder or bowel changes, which can signal a nerve problem
- Orgasm with little or no semen, or cloudy urine afterward
- Pain during sex or ejaculation, or blood in the semen
- Known or suspected diabetes or thyroid disease
- Difficulty conceiving after a year of trying
Source: Cleveland Clinic — DE overview; NHS — Ejaculation problems
If delayed ejaculation is affecting your sex life or plans for a family, you can arrange a confidential assessment with our urologist-andrologist, Assoc. Prof. Dr. Zülfü Sertkaya, through WhatsApp. The plan and any cost depend on what the assessment finds.
FAQs about delayed ejaculation
Is delayed ejaculation curable?
Often, yes, when the cause can be removed. Delayed ejaculation caused by a medicine, alcohol or drugs often improves once the substance is changed or reduced, and psychological causes may respond to therapy. DE from severe nerve damage or ageing is harder to reverse, but fertility options and vibratory stimulation can still help.
Source: Cleveland Clinic — DE overview
Do all antidepressants cause delayed ejaculation?
Not all, and not in every man. SSRIs are the classic culprits because serotonin slows the ejaculation reflex. If you notice the problem, your prescriber may lower the dose, switch drugs, or add a medicine such as bupropion, which showed benefit at 150 mg twice daily in a Cochrane review. Do not stop an antidepressant abruptly on your own.
Source: PubMed — Taylor et al. (Cochrane 2013)
Can low testosterone cause delayed ejaculation?
It may contribute, but the link is uncertain. The EAU says newer studies have not confirmed an association between testosterone and ejaculation time, and a randomized trial found testosterone gel no better than placebo for ejaculatory symptoms. The AUA still allows normalizing a truly low level, so testing makes sense if you also have low desire or fatigue.
Source: PubMed — Paduch et al. (J Clin Endocrinol Metab 2015)
Is there a pill for delayed ejaculation?
No pill has FDA approval for delayed ejaculation. Doctors sometimes prescribe cabergoline, bupropion, buspirone, amantadine or cyproheptadine off-label, but the EAU says none has proven efficacy and a provider survey put overall success at about 40%. Any such medicine should be chosen for your specific cause.
Source: EAU Guidelines — Disorders of ejaculation
Can masturbation habits cause delayed ejaculation?
They can play a part. The AUA notes that idiosyncratic or very forceful masturbation is linked to trouble climaxing with a partner, because partnered sex feels different. Sex therapists use masturbation retraining, gradually changing grip, speed and frequency, as part of psychological treatment described by the EAU.
Source: AUA/SMSNA — Disorders of Ejaculation Guideline
Can I still have children if I have delayed ejaculation?
Usually there are options. Treating the cause may restore ejaculation. If not, penile vibratory stimulation can collect semen, and the EAU names electroejaculation as the next step, with surgical sperm retrieval if that fails. The sperm can then be used for assisted reproduction such as IVF.
Source: EAU Guidelines — Disorders of ejaculation
Medically reviewed by Assoc. Prof. Dr. Zülfü Sertkaya, urologist and andrologist (FEBU), Istanbul. Last reviewed: October 2026.
This article is for general information and does not replace an individual consultation with a qualified doctor.
- EAU — Sexual and Reproductive Health Guidelines — Disorders of ejaculation
- AUA/SMSNA — Disorders of Ejaculation: An AUA/SMSNA Guideline
- PubMed — J Urol 2022 — Shindel et al. Disorders of Ejaculation: An AUA/SMSNA Guideline
- ISSM — How Long Is Considered Delayed Ejaculation?
- ISSM — Characteristics of Men Who Report Delayed Ejaculation Symptoms
- NHS — Ejaculation problems
- Cleveland Clinic — Delayed Ejaculation: Causes, Diagnosis & Treatment
- PMC — Transl Androl Urol 2016 — Jiann. The office management of ejaculatory disorders
- PubMed — World J Mens Health 2018 — Abdel-Hamid & Ali. Delayed Ejaculation: Pathophysiology, Diagnosis, and Treatment
- PubMed — Transl Androl Urol 2016 — Abdel-Hamid et al. The drug treatment of delayed ejaculation
- PubMed — Sex Med 2016 — Hollander et al. Cabergoline in the treatment of male orgasmic disorder
- PubMed — Cochrane Database Syst Rev 2013 — Taylor et al. Strategies for managing sexual dysfunction induced by antidepressant medication
- PubMed — J Clin Endocrinol Metab 2005 — Carani et al. Prevalence of sexual symptoms in male hypo- and hyperthyroid patients
- PubMed — J Clin Endocrinol Metab 2015 — Paduch et al. Testosterone replacement in androgen-deficient men with ejaculatory dysfunction: an RCT


