

The selective dorsal neurectomy premature ejaculation debate comes down to one question: does cutting some branches of the dorsal penile nerve help men last longer, and at what cost? Small trials, mostly from China and South Korea, report that ejaculation time rises roughly three- to four-fold after surgery, but the European, American and international sexual medicine guidelines still advise against it outside a clinical trial because the nerve damage cannot be undone and long-term safety data are thin. This page is the evidence review behind our selective dorsal neurectomy treatment page: what the studies actually measured, what the guidelines say, and how the procedure compares with first-line options.
Source: EAU — Sexual and Reproductive Health Guidelines (disorders of ejaculation); J Sex Med (PubMed) — Culha et al. 2025, selective dorsal neurectomy/cryoablation meta-analysis
- A 2025 meta-analysis of 7 studies (235 men) found that selective dorsal neurectomy or cryoablation lengthened intravaginal ejaculation latency time (IELT) by a mean of 147 seconds, with an 11.2% adverse-event rate and only short-term follow-up.
- The EAU says “Do not perform dorsal neurectomy as more safety data are warranted”; the AUA/SMSNA calls surgery for PE experimental; the ISSM does not recommend it because of possible permanent loss of sexual function.
- Reported dorsal neurectomy complications include recurrence of PE (about 10%), glans pain or altered sensation (about 4–8%), and rare erectile problems; no standard technique exists for how many nerve branches to cut.
- Cryoneurolysis freezes the nerve instead of cutting it; a 2026 Istanbul cohort of 108 men reported IELT rising from 54 to 231 seconds, but most men needed repeat sessions and there was no control group.
- Guideline first-line care is dapoxetine or a lidocaine-prilocaine spray, with daily SSRIs and behavioral therapy as alternatives; dorsal neurectomy is a last resort for a small, carefully selected group.
- What selective dorsal neurectomy is and how it is meant to work
- Selective dorsal neurectomy premature ejaculation guidelines: EAU, AUA and ISSM
- Selective dorsal neurectomy premature ejaculation evidence: the trials
- Cryoneurolysis: freezing the nerve instead of cutting it
- Selective dorsal neurectomy premature ejaculation risks and complications
- Who might be a candidate, and who should not have it
- What the procedure and recovery involve
- How surgery compares with first-line treatments
- When to see a doctor
- FAQs about selective dorsal neurectomy for premature ejaculation
What selective dorsal neurectomy is and how it is meant to work
Premature ejaculation (PE) is the most common male sexual complaint: Cleveland Clinic estimates that 30% to 40% of men experience it at some point, and about 1 in 5 men aged 18 to 59 report it. The International Society for Sexual Medicine (ISSM) defines lifelong PE as ejaculation that always or nearly always happens before or within about one minute of penetration, from the first sexual experiences onward, with distress and little sense of control. The American guideline uses a broader “about 2 minutes” threshold.
Source: Cleveland Clinic — Premature ejaculation; Sexual Medicine (PMC) — Althof et al. 2014, ISSM guidelines for premature ejaculation
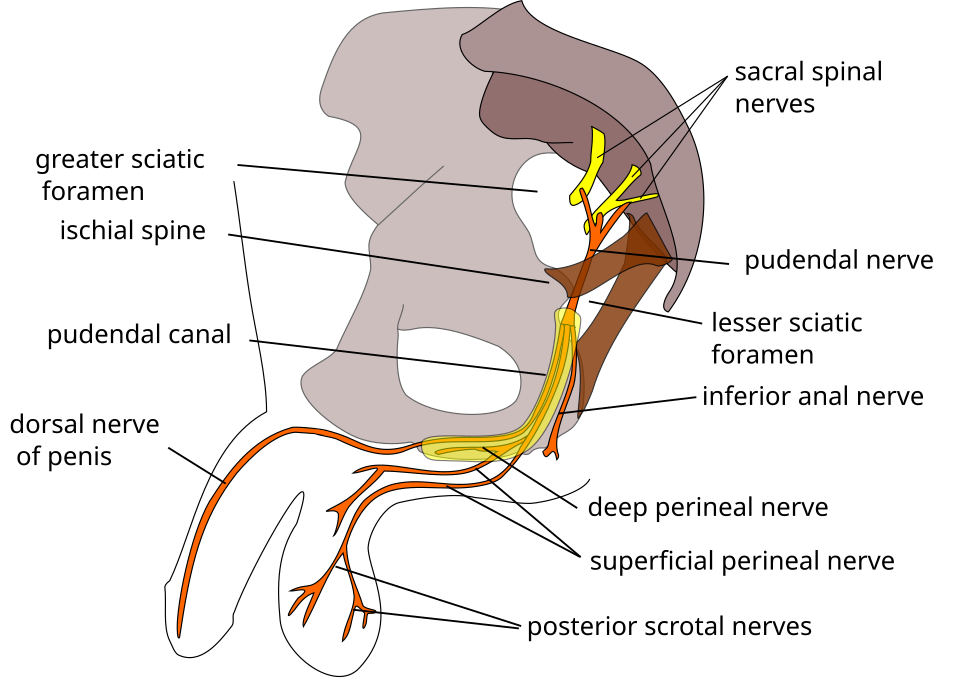
One theory of lifelong PE is that the head of the penis sends sensory signals to the spinal cord too strongly or too quickly. The dorsal nerve of the penis, the deepest branch of the pudendal nerve, carries most of that sensation along the top of the shaft to the glans. Selective dorsal neurectomy (also called selective dorsal neurotomy, SDN) cuts some of its branches near the coronal sulcus, just behind the glans, so that fewer signals reach the ejaculation reflex. The idea was first proposed by Tulli and colleagues in 1994 for men who did not respond to conventional treatment, and it spread mainly in South Korea and later China.
A 2019 anatomical study supports the rationale: men with lifelong PE had more, and thicker, dorsal nerve branches than men without PE. The word “selective” matters because surgeons leave the main trunks intact and remove only a share of the smaller branches. How many branches a dorsal neurectomy should cut has never been standardized: Korean surgeons have typically removed two or three lateral branches on each side, while some Chinese series removed 3 to 10 branches and preserved the two main ones.
Source: J Sex Med (PubMed) — Liu et al. 2019, anatomic basis and clinical effect of selective dorsal neurectomy; Translational Andrology and Urology — Moon 2016, is there a place for surgical treatment of premature ejaculation?
Selective dorsal neurectomy premature ejaculation guidelines: EAU, AUA and ISSM

Every major guideline body takes a cautious or negative position on dorsal neurectomy for PE; here are their exact words.
European Association of Urology (EAU)
The EAU Sexual and Reproductive Health guideline states: “Do not perform dorsal neurectomy as more safety data are warranted” (weak recommendation). The same chapter advises using hyaluronic acid glans injection “with caution” (weak) and gives a strong recommendation for dapoxetine or a lidocaine-prilocaine spray as first-line treatment for lifelong PE.
Source: EAU — Sexual and Reproductive Health Guidelines (disorders of ejaculation)
American Urological Association / SMSNA
Guideline Statement 15 of the AUA/SMSNA Disorders of Ejaculation guideline says surgical management of PE, including injection of bulking agents, “should be considered experimental” and should only take place within an ethics-board-approved clinical trial. The panel warns that “surgery may be associated with permanent loss of penile sensation” and that “there may be as yet undefined chronic disabilities” after dorsal penile neurectomy. It also notes that the main randomized trial showing benefit (4.29 versus 0.82 minutes IELT for dorsal neurectomy plus circumcision versus circumcision alone) came from a single center and “has not been reproduced in other centers”.
Source: AUA/SMSNA — Disorders of Ejaculation guideline
International Society for Sexual Medicine (ISSM)
The ISSM guideline lists “selective dorsal nerve neurotomy or glans penis augmentation using hyaluronic acid gel” as procedures that may be associated with permanent loss of sexual function and states they are not recommended for the management of PE. For dorsal penile nerve cryoablation and neuromodulation, it assigns level-of-evidence 4 and says safety “needs to be determined before this procedure can be recommended”. A Korean review noted that this position created confusion among Korean doctors and legal problems for dissatisfied patients after dorsal neurectomy.
Source: Sexual Medicine (PMC) — Althof et al. 2014, ISSM guidelines for premature ejaculation; Translational Andrology and Urology — Moon 2016, is there a place for surgical treatment of premature ejaculation?
Selective dorsal neurectomy premature ejaculation evidence: the trials
The published dorsal neurectomy evidence is small, comes from a handful of Asian centers, and measures outcomes for months rather than years. Still, the direction of the results is consistent: IELT goes up. The question the guidelines raise is whether that gain is worth an irreversible change to penile sensation.
Randomized and controlled studies
Zhang and colleagues (2012) randomized 101 men to selective resection of dorsal nerves plus circumcision (40 men) or circumcision alone (61). IELT rose from 1.1 to 3.8 minutes after dorsal neurectomy, while the circumcision-only group barely changed (1.2 to 1.5 minutes); erectile function scores were unaffected. Liu and colleagues (2019) randomized 96 men with lifelong PE and redundant foreskin to neurectomy plus circumcision or circumcision alone; post-operative IELT was 257.7 seconds versus 49.3 seconds, with no permanent glans numbness, infection or hematoma reported. Both trials were single-center with limited follow-up.
Source: Int J Androl (PubMed) — Zhang et al. 2012, selective resection of dorsal nerves of penis for premature ejaculation; J Sex Med (PubMed) — Liu et al. 2019, anatomic basis and clinical effect of selective dorsal neurectomy
Tang and colleagues (Nanjing, 2023) randomized 120 men with the “penile sensory hyperexcitability” type of lifelong PE to neurectomy with or without intraoperative nerve monitoring, which measures sensory signals while branches are removed one at a time. At 3 months, 63.6% of monitored patients reached an IELT of 300 seconds or more compared with 34.0% without monitoring, and complications were 7.3% versus 20.8%; the unmonitored group included three men with mild erectile dysfunction. Surgeons kept at least one branch on each side. The authors called for larger, multicenter, long-term dorsal neurectomy trials.
Meta-analysis and surveys
The first systematic review and meta-analysis, published in the Journal of Sexual Medicine in 2025, pooled 7 studies with 235 patients treated by selective dorsal neurectomy or cryoablation. IELT improved by a mean difference of 147.47 seconds, erectile function (IIEF-5) showed no meaningful change, and the pooled adverse-event rate was 11.17%. The authors concluded that the procedure “is controversial as a treatment option for PE” and asked for standard protocols and longer follow-up.
Real-world experience is larger than the trial data. A 2012 nationwide Korean survey answered by 527 urologists found that 72.9% had prior experience of dorsal neurectomy and 54.3% used surgery to manage PE patients. Urologists estimated that 57% of their patients were satisfied and 3.4% dissatisfied, with recurrence of PE (about 10%) the most common problem. The survey authors themselves wrote that surgery was being used “despite the lack of scientific evidence” and that no standard procedure existed.
Source: J Sex Med (PubMed) — Culha et al. 2025, selective dorsal neurectomy/cryoablation meta-analysis; World Journal of Men’s Health (PMC) — Yang et al. 2013, Korean nationwide survey on premature ejaculation practice
| Study | Design and size | Ejaculation time result | Safety signal |
|---|---|---|---|
| Zhang 2012 | RCT, 40 neurectomy vs 61 circumcision | IELT 1.1 → 3.8 min vs 1.2 → 1.5 min | Erectile function unchanged |
| Liu 2019 | RCT, 48 vs 48 men with lifelong PE | 257.7 s vs 49.3 s after surgery | No permanent numbness reported |
| Tang 2023 | RCT, 120 men, nerve monitoring vs none | ≥300 s in 63.6% vs 34.0% at 3 months | Complications 7.3% vs 20.8% |
| Prologo 2013 | Single-arm cryoablation, 24 men | 54.7 s → 140.9 s at 1 year | 83% would repeat it |
| Basaga 2026 | Retrospective cryoneurolysis cohort, 108 men | 54.4 s → 231.3 s at 12 months | 75.9% needed a second session |
| Culha 2025 | Meta-analysis, 7 studies, 235 men | Mean IELT gain 147.47 s | Adverse events 11.17% |
Source: Translational Andrology and Urology — Ambusaidi et al. 2023, the role of surgical therapy in premature ejaculation; J Sex Med (PubMed) — Basaga et al. 2026, selective dorsal cryoneurolysis in 108 men with lifelong premature ejaculation
Cryoneurolysis: freezing the nerve instead of cutting it
Because the main objection to dorsal neurectomy is irreversibility, researchers have tested ways to quiet the dorsal nerve without removing it. In 2013, Prologo and colleagues in the United States performed CT-guided cryoablation of one dorsal penile nerve in 24 men. Baseline IELT was 54.7 seconds; it was 182.5 seconds at 6 months and 140.9 seconds at 1 year, and 83% of men said they would repeat the procedure. The authors reported no procedure-related complications, although a later review noted temporary erection weakness in four men that improved. The effect clearly faded over the year, which is the trade-off of a potentially reversible technique.
Source: J Vasc Interv Radiol (PubMed) — Prologo et al. 2013, CT-guided cryoablation of the dorsal penile nerve for premature ejaculation; Translational Andrology and Urology — Moon 2016, is there a place for surgical treatment of premature ejaculation?
The largest series so far is a 2026 retrospective cohort from Istanbul, co-authored by our urologist-andrologist Assoc. Prof. Dr. Zülfü Sertkaya, of 108 men with lifelong PE treated with selective dorsal cryoneurolysis between January 2024 and January 2025. Geometric mean IELT rose from 54.4 seconds to 231.3 seconds at 12 months, the Premature Ejaculation Diagnostic Tool score fell from 14.3 to 8.4, and penile vibration thresholds roughly doubled, confirming reduced sensation. Procedure discomfort affected 7.4% of men, 10.2% still had PE at 12 months, and no erectile dysfunction, anorgasmia, persistent numbness or infection was recorded. The caveats: 75.9% needed a second session and 20.4% a third, there was no control group, and the authors describe the technique as investigational pending randomized trials.
That randomized trial now exists. Biruni University in Istanbul registered an open-label study (NCT07879105) that randomized 117 men with lifelong PE to one cryoneurolysis session plus daily sertraline 50 mg, tadalafil 5 mg and behavioral training, or the same medication and training alone, with the change in stopwatch IELT at 3 months as the primary outcome. The study was completed in May 2026; until its results are published, cryoneurolysis remains “promising but unproven”, with the advantage that it removes no tissue.
Source: J Sex Med (PubMed) — Basaga et al. 2026, selective dorsal cryoneurolysis in 108 men with lifelong premature ejaculation; ClinicalTrials.gov — NCT07879105, dorsal penile nerve cryoneurolysis for lifelong PE
Selective dorsal neurectomy premature ejaculation risks and complications

The dorsal neurectomy complication rates below come from the Korean and Chinese series and the 2025 meta-analysis. They are probably underestimates of long-term harm, because most studies did not test sensation formally and stopped following patients after a few months.
- Recurrence of PE: the most common disappointment, reported in about 10% of patients in the Korean nationwide survey. Nerve branches can regenerate, and the brain and spinal cord adapt.
- Glans pain, tingling or numbness: 3.8% of patients in the Korean survey; 8.1% numbness in one 74-patient series; 4.9% glans pain in a 143-patient series. The AUA warns that loss of penile sensation can be permanent.
- Swelling, wound separation and scarring: penile edema in 4.2% and wound dehiscence in 2.1% of one series; penile curvature from scarring is described as rare.
- Erectile dysfunction: 0.4% in the Korean survey, and three cases of mild ED among 53 unmonitored patients in the 2023 Nanjing trial; the meta-analysis found no meaningful change in average erectile scores.
- Delayed ejaculation or reduced orgasm quality: 0.6% in one series; the risk of over-correction is the reason surgeons try to cut as few branches as possible.
- Any adverse event: 11.17% pooled across the 7 studies in the 2025 meta-analysis; 11.8% in the largest single Korean series.
Source: Translational Andrology and Urology — Moon 2016, is there a place for surgical treatment of premature ejaculation?; World Journal of Men’s Health (PMC) — Yang et al. 2013, Korean nationwide survey on premature ejaculation practice; AUA/SMSNA — Disorders of Ejaculation guideline
One further risk is rarely counted in studies: regret. Medication can be stopped and a spray washed off, but a resected nerve branch cannot be reattached, and removing sensation does nothing for the anxiety or relationship factors that often drive PE. This is why every guideline asks for proper trials, and why any surgeon offering the operation should document sensation testing, IELT and questionnaires before and after.
Source: AUA/SMSNA — Disorders of Ejaculation guideline; Sexual Medicine (PMC) — Althof et al. 2014, ISSM guidelines for premature ejaculation
Who might be a candidate, and who should not have it
If a man and his urologist consider dorsal neurectomy at all, the published series describe a narrow profile: lifelong PE present since the first sexual experiences, an IELT of around one minute or less measured with a stopwatch, normal erections, no prostatitis or hormonal cause, and an inadequate response to properly tried first-line treatment. The Nanjing team went further and restricted surgery to men whose nerve-conduction tests showed a “penile sensory hyperexcitability” pattern, which may explain their higher response rate.
Surgery is a poor fit for acquired PE (a sudden change after years of normal control), for men whose PE is linked to erectile dysfunction, anxiety or a new relationship, and for anyone who has not yet tried dapoxetine, a daily SSRI, a lidocaine-prilocaine spray or behavioral training. The EAU is explicit that erectile dysfunction, other sexual dysfunction and genitourinary infection must be treated first. Our guide to premature ejaculation pills and our review of the numbing spray for premature ejaculation explain what a fair trial of those options looks like.
Source: EAU — Sexual and Reproductive Health Guidelines (disorders of ejaculation); Asian Journal of Andrology (PMC) — Tang et al. 2023, intraoperative neurophysiological monitoring in selective dorsal neurotomy
What the procedure and recovery involve
Dorsal neurectomy techniques vary between centers, which is itself one of the criticisms. In the published series the operation is done through a circumcision-type incision at the coronal sulcus: the surgeon identifies the dorsal nerve branches, removes a short segment (about 0.5 cm in the Zhang protocol) from a selected number of them, and preserves the main trunks. Circumcision is usually performed at the same time, which is why trials used circumcision alone as the comparison. With intraoperative monitoring, each branch is tested before removal and the surgeon stops once the sensory signal has slowed to the target range; this lengthened median operating time from 60 to 90 minutes in the Nanjing trial.
Recovery follows a circumcision pattern: swelling and tenderness for one to two weeks and no sexual activity until the wound has healed, with outcomes in the studies measured at 3, 6 and 12 months. Cryoneurolysis is a needle procedure rather than an open operation; in the Istanbul trial protocol a probe cools four dorsal sites to about minus 78 degrees Celsius through a single puncture, and most men in the 2026 cohort returned for a second session.
Source: Translational Andrology and Urology — Moon 2016, is there a place for surgical treatment of premature ejaculation?; Asian Journal of Andrology (PMC) — Tang et al. 2023, intraoperative neurophysiological monitoring in selective dorsal neurotomy; ClinicalTrials.gov — NCT07879105, dorsal penile nerve cryoneurolysis for lifelong PE
How surgery compares with first-line treatments
Most men never need to think about dorsal neurectomy. The NHS lists daily SSRIs (which take one to two weeks to reach full effect), on-demand dapoxetine, topical anesthetics, thicker condoms and psychosexual counselling with the squeeze and stop-start methods as the standard pathway. Every one of these is reversible, and several can be combined.
| Option | Guideline position | Reversible? | Main drawbacks |
|---|---|---|---|
| Dapoxetine (on demand) | EAU first-line, strong | Yes | Nausea, dizziness; taken 1–3 h before sex |
| Lidocaine-prilocaine spray | EAU first-line, strong | Yes | Reduced sensation, partner transfer |
| Daily SSRI (off-label) | EAU second-line, strong; AUA first-line | Yes | Daily dosing, mood and libido effects |
| Behavioral therapy | Recommended with drugs (EAU weak, AUA moderate) | Yes | Needs practice and partner involvement |
| Hyaluronic acid glans injection | EAU “with caution”, weak; ISSM not recommended | Partly (filler is absorbed) | Effect fades; limited multicenter data |
| Cryoneurolysis | Investigational; RCT pending | Likely, nerve may recover | Repeat sessions, effect may fade |
| Selective dorsal neurectomy | EAU “do not perform”; AUA experimental; ISSM not recommended | No | Irreversible sensory loss, ~10% recurrence |
Source: NHS — Ejaculation problems; EAU — Sexual and Reproductive Health Guidelines (disorders of ejaculation); AUA/SMSNA — Disorders of Ejaculation guideline
Our view mirrors the guidelines: medication, spray and behavioral work first, in combination and for long enough to judge; then, for the small group who still ejaculate within a minute, a frank discussion of the investigational options, starting with the least destructive. The full menu is on our premature ejaculation treatment page, and the pillar premature ejaculation guide covers causes and diagnosis in depth.
If you would like a confidential opinion on whether you fall into that small group, you can message our urologist-andrologist on WhatsApp. Send your stopwatch IELT and treatment history, and you will get an honest answer about whether any procedure is worth discussing.
When to see a doctor
The NHS advises seeing a doctor whenever an ejaculation problem is persistent, and Cleveland Clinic adds that PE which causes anxiety, low mood or strain in a relationship deserves specialist help. A urologist can confirm whether the problem is lifelong or acquired and check for erectile dysfunction, prostatitis, thyroid disease or medication effects. Seek care promptly if you notice any of the following:
- PE that started suddenly together with weaker erections, pain on ejaculation, or blood in the semen.
- Burning, discharge, fever or pelvic pain, which can point to prostatitis or infection that must be treated before any PE therapy.
- Persistent numbness, pain, swelling, wound opening or a new bend in the penis after any penile surgery or injection, including nerve surgery performed elsewhere.
- Distress strong enough to make you avoid intimacy or consider an irreversible procedure, which is exactly when a second opinion is most valuable.
Source: NHS — Ejaculation problems; Cleveland Clinic — Premature ejaculation
FAQs about selective dorsal neurectomy for premature ejaculation
Does selective dorsal neurectomy cure premature ejaculation?
No treatment cures lifelong PE outright. In the trials, dorsal neurectomy raised average ejaculation time three- to four-fold, but about 10% of men saw their PE return, and follow-up rarely exceeded a year. The 2025 meta-analysis calls the operation controversial and asks for longer studies before anyone describes it as a cure.
Source: J Sex Med (PubMed) — Culha et al. 2025, selective dorsal neurectomy/cryoablation meta-analysis
Why do the guidelines advise against the operation if the trials are positive?
Because the evidence comes from a few small, single-center studies with short follow-up, and the procedure is irreversible. The AUA/SMSNA panel points to possible permanent loss of penile sensation and “undefined chronic disabilities”, and asks that surgery take place only inside an ethics-approved trial. Guideline committees weigh safety as heavily as efficacy.
Source: AUA/SMSNA — Disorders of Ejaculation guideline
Will I lose feeling in the penis after dorsal neurectomy?
Reduced glans sensitivity is the intended effect, and most men keep normal orgasm and erection. Unwanted numbness, tingling or glans pain affected roughly 4% to 8% of patients in the Korean series, and sensation testing was rarely done in the Chinese trials, so the true rate of long-term change is unknown.
Can selective dorsal neurectomy cause erectile dysfunction?
Rarely. The Korean survey put erectile dysfunction at 0.4%, the meta-analysis found no meaningful change in IIEF-5 scores, and three men in the unmonitored arm of the 2023 Nanjing trial developed mild ED. The dorsal nerve mainly carries sensation, not the erection signal, but injury or scarring can still interfere.
Is cryoneurolysis safer than cutting the nerve?
It is less destructive, and the 108-man Istanbul cohort reported no erectile dysfunction, persistent numbness or infection. The price is durability: three-quarters of men needed a second session and the 2013 US cryoablation study saw the effect fade by one year. A randomized trial completed in 2026 should clarify its place.
Source: J Sex Med (PubMed) — Basaga et al. 2026, selective dorsal cryoneurolysis in 108 men with lifelong premature ejaculation; J Vasc Interv Radiol (PubMed) — Prologo et al. 2013, CT-guided cryoablation of the dorsal penile nerve for premature ejaculation
Does circumcision alone help premature ejaculation?
No. Two meta-analyses found no difference in ejaculation time, erectile function or pain between circumcised and uncircumcised men, and the circumcision-only arms of the neurectomy trials improved by only a few seconds. Circumcision is performed alongside dorsal neurectomy for surgical access, not as a treatment in itself.
Source: Translational Andrology and Urology — Ambusaidi et al. 2023, the role of surgical therapy in premature ejaculation; Int J Androl (PubMed) — Zhang et al. 2012, selective resection of dorsal nerves of penis for premature ejaculation
What should I try before considering nerve surgery?
A fair trial of the guideline options: on-demand dapoxetine or a daily SSRI for several weeks, a lidocaine-prilocaine spray, thicker condoms, and behavioral training such as the squeeze technique, ideally in combination and with your partner involved. Any erectile dysfunction, prostatitis or hormonal problem should be treated first, as the EAU requires.
Source: NHS — Ejaculation problems; EAU — Sexual and Reproductive Health Guidelines (disorders of ejaculation)
How much does selective dorsal neurectomy cost?
None of the cited studies or guidelines report dorsal neurectomy prices. The cost depends on the country, the anesthesia, whether circumcision or nerve monitoring is included, and above all on the assessment that decides whether you are a candidate; a free, confidential WhatsApp consultation is the simplest way to get a personal answer.
Source: J Sex Med (PubMed) — Culha et al. 2025, selective dorsal neurectomy/cryoablation meta-analysis
Medically reviewed by Assoc. Prof. Dr. Zülfü Sertkaya, urologist and andrologist (FEBU), Istanbul. Last reviewed: November 2026.
This article is for general information and does not replace an individual consultation with a qualified doctor.
- EAU — Sexual and Reproductive Health Guidelines (disorders of ejaculation)
- AUA/SMSNA — Disorders of Ejaculation guideline
- Sexual Medicine (PMC) — Althof et al. 2014, ISSM guidelines for premature ejaculation
- J Sex Med (PubMed) — Culha et al. 2025, selective dorsal neurectomy/cryoablation meta-analysis
- Int J Androl (PubMed) — Zhang et al. 2012, selective resection of dorsal nerves of penis for premature ejaculation
- J Sex Med (PubMed) — Liu et al. 2019, anatomic basis and clinical effect of selective dorsal neurectomy
- Asian Journal of Andrology (PMC) — Tang et al. 2023, intraoperative neurophysiological monitoring in selective dorsal neurotomy
- World Journal of Men's Health (PMC) — Yang et al. 2013, Korean nationwide survey on premature ejaculation practice
- Translational Andrology and Urology — Moon 2016, is there a place for surgical treatment of premature ejaculation?
- Translational Andrology and Urology — Ambusaidi et al. 2023, the role of surgical therapy in premature ejaculation
- J Vasc Interv Radiol (PubMed) — Prologo et al. 2013, CT-guided cryoablation of the dorsal penile nerve for premature ejaculation
- J Sex Med (PubMed) — Basaga et al. 2026, selective dorsal cryoneurolysis in 108 men with lifelong premature ejaculation
- ClinicalTrials.gov — NCT07879105, dorsal penile nerve cryoneurolysis for lifelong PE
- NHS — Ejaculation problems
- Cleveland Clinic — Premature ejaculation


