

Micro TESE (microdissection testicular sperm extraction) is an operation that searches the inside of the testicle under a high-powered microscope for the few small areas that still make sperm, so the sperm can be used for ICSI. It is the main option for men with non-obstructive azoospermia, where the testicles produce little or no sperm and none reaches the semen. It is done under general anesthesia, usually as a day case, and finds sperm in roughly half of men, depending on the cause. For the full picture of zero sperm counts, causes and tests, start with our guide to azoospermia.
Sources: Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction); EAU — Sexual and Reproductive Health Guidelines (male infertility chapter); NHS — Infertility: treatment
- Microdissection TESE (micro TESE) is recommended by the EAU and AUA/ASRM guidelines as the sperm retrieval method for non-obstructive azoospermia (NOA); needle aspiration (TESA) is not advised in NOA.
- In micro TESE, the surgeon opens the testicle and uses 24–36× magnification to pick out the wider, more opaque tubules, which are the ones most likely to contain sperm.
- Large meta-analyses report sperm retrieval in about 46–47% of men with NOA overall, with wide variation by testicular histology and cause.
- Recovery from micro TESE usually takes a few days off work and a few weeks in total; testosterone may dip for months but tends to return to about 95% of baseline by 18 months.
- Genetic tests come first: complete AZFa or AZFb Y-chromosome deletions mean micro TESE should not be performed.
- What is micro TESE?
- Who is a candidate for micro TESE?
- Micro TESE vs conventional TESE vs TESA
- Preparing for micro TESE
- How micro TESE is performed, step by step
- Micro TESE success rate and what predicts it
- Recovery after the operation
- Risks, complications and testosterone
- After the result: ICSI, repeat surgery or donor sperm
- When to see a doctor
- FAQs about micro TESE
What is micro TESE?
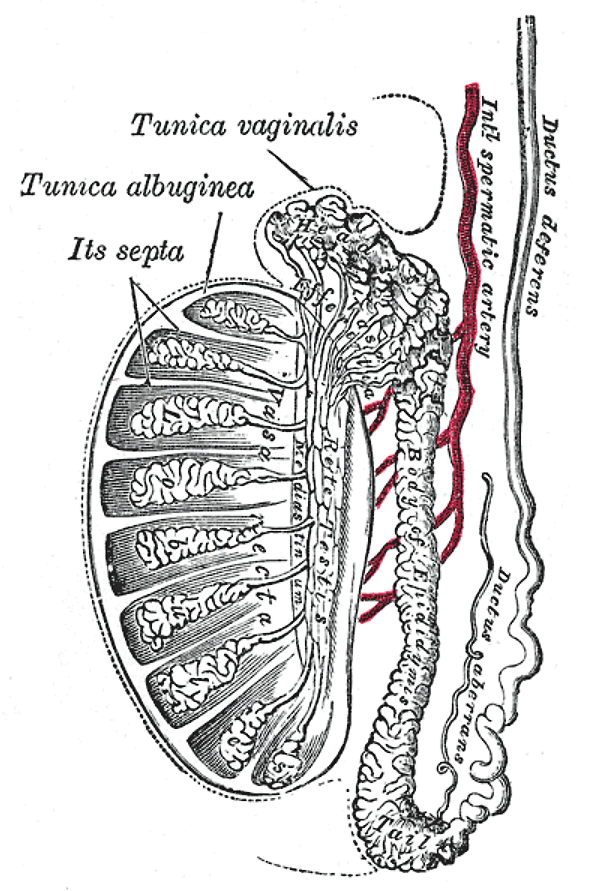
Sperm are made inside hundreds of tiny coiled tubes in the testicle called seminiferous tubules. In many men with non-obstructive azoospermia, most tubules contain only support cells (Sertoli cells), but a few scattered pockets may still produce sperm. Those pockets are invisible from the outside, so older “blind” biopsy methods could miss them or remove a lot of healthy tissue to find them.
Micro TESE was described in 1999 by Peter Schlegel at Cornell. His idea was simple: tubules that contain developing sperm cells are larger and more opaque than tubules with Sertoli cells alone, and an operating microscope can show the difference. In his first series, the share of men in whom sperm were found rose from 45% to 63% after the technique was introduced, and the microdissected samples gave more sperm from far less tissue (an average of 9.4 mg versus 720 mg in standard biopsies).
Cleveland Clinic summarizes the three goals of micro TESE: retrieve the best-quality sperm, retrieve enough to fertilize an egg, and limit damage to the testicle. Any sperm found are used for ICSI (intracytoplasmic sperm injection), in which an embryologist injects a single sperm directly into each egg.
Sources: Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction); HFEA — Intracytoplasmic sperm injection (ICSI)
Who is a candidate for micro TESE?
Micro TESE is designed for men whose testicles make very little sperm, not for men whose sperm are simply blocked. Our azoospermia guide explains how doctors separate obstructive from non-obstructive cases; in short, obstruction usually comes with normal hormones and normal-sized testicles, and simpler needle or epididymal methods are often enough there.
Typical candidates include men with:
- Non-obstructive azoospermia (NOA) confirmed on at least two semen analyses, after a full hormone, genetic and ultrasound work-up.
- Klinefelter syndrome (47,XXY), where the EAU reports that sperm can be recovered in up to 50% of cases.
- AZFc Y-chromosome microdeletions, where testicular sperm is found in 50–75% of men.
- Persistent azoospermia after chemotherapy or radiotherapy; the AUA/ASRM guideline states that men in this situation should be told TESE is a treatment option.
- A previous failed TESA or conventional TESE, as a “salvage” attempt.
- A history of undescended testicles, which the EAU lists among factors linked to higher retrieval chances.
Sources: EAU — Sexual and Reproductive Health Guidelines (male infertility chapter); AUA/ASRM — Diagnosis and Treatment of Infertility in Men: Guideline Part II
There is one clear exclusion. The EAU makes a strong recommendation not to operate on men with complete AZFa or AZFb deletions, because the chance of finding sperm is essentially zero. This is why a karyotype and Y-chromosome microdeletion test, with genetic counselling, should always come before micro TESE.
Source: EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
Micro TESE vs conventional TESE vs TESA
Retrieval methods differ in how much of the testicle is explored and whether a microscope is used. The EAU now advises against needle methods (TESA or fine-needle aspiration) in NOA and names microdissection as the treatment of choice, although that particular recommendation is graded “weak” because the head-to-head evidence is mixed.
| Feature | TESA (needle) | Conventional TESE | Micro TESE |
|---|---|---|---|
| How it works | Needle passed through the skin into the testicle | One or more open biopsies taken without magnification | Testicle opened widely; tubules selected under a microscope |
| Retrieval rate in NOA (EAU) | 11–60%; not recommended | About 50% in single-arm studies | 52% vs 35% for TESE in pooled case-control data; 43% vs 22% for TESA in one trial |
| Tissue removed | Small, blind samples | Larger blind samples | Small, targeted samples |
| Main drawback | Misses patchy sperm production | More hematoma and scarring | Longer surgery, general anesthesia, specialist skill |
| Best suited to | Obstructive azoospermia | Where microsurgery is not available | Non-obstructive azoospermia |
Source: EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
To be honest about the evidence: the largest meta-analysis (Corona et al., 2019, 117 studies and 21,404 men) found the same retrieval rate of 46% for conventional and microdissection TESE, while comparative studies favor the microscope. A systematic review from Leuven reported a range of 42.9–63% with the microscope versus 16.7–45% with conventional TESE, and fewer complications on ultrasound after the microsurgical approach. No large randomized trial has settled the question yet.
Sources: Hum Reprod Update (PubMed) — Corona et al. 2019, Sperm recovery and ICSI outcomes in NOA; Andrology (PubMed) — Deruyver et al. 2014, Micro-TESE vs conventional TESE in NOA: a systematic review
Preparing for micro TESE
Tests and counselling
Before micro TESE your urologist will review two or more semen analyses, hormones (FSH, LH, total testosterone), a karyotype, Y-chromosome microdeletion testing and a scrotal ultrasound. If your last test showed zero sperm, our article on semen analysis explains why the sample must be repeated and centrifuged before the diagnosis is accepted.
Source: EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
Hormone treatment before surgery
Some clinics give clomiphene, aromatase inhibitors or hCG before micro TESE to raise testosterone. The evidence is limited. The AUA/ASRM guideline says men with NOA should be told about the limited data supporting this, and the EAU advises against routine hormonal stimulation before TESE, as no randomized trial has shown a benefit in idiopathic NOA. Men with low hormone production from the pituitary (hypogonadotropic hypogonadism) are different: they are treated with gonadotropins first, and many never need surgery.
Sources: AUA/ASRM — Diagnosis and Treatment of Infertility in Men: Guideline Part II; EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
Never take testosterone, or anabolic steroids, while trying to conceive. The AUA/ASRM guideline states that testosterone on its own should not be prescribed to a man who wants current or future fertility; read more in our guide to testosterone replacement therapy.
Source: AUA/ASRM — Diagnosis and Treatment of Infertility in Men: Guideline Part II
Varicocele and timing
If you also have a palpable varicocele, repairing it first is sometimes discussed. The EAU notes that sperm retrieval rates were higher after repair in a meta-analysis, but calls the evidence low quality, and the AUA/ASRM guideline says there is no definitive evidence supporting repair before assisted reproduction. Because any benefit takes at least 3–6 months, surgeons generally avoid delaying sperm retrieval when the female partner is older. See our varicocele guide for details.
Sources: EAU — Sexual and Reproductive Health Guidelines (male infertility chapter); AUA/ASRM — Diagnosis and Treatment of Infertility in Men: Guideline Part II; J Clin Med (PMC) — Colpi & Caroppo 2021, Performing microdissection TESE: surgical pearls
Fresh or frozen sperm?
Micro TESE can be timed with the partner’s egg collection so that fresh sperm are used, or it can be done first and the sperm frozen. The AUA/ASRM guideline says either fresh or frozen sperm may be used for ICSI. Some high-volume centers prefer fresh sperm because only about a third of frozen-thawed testicular sperm remain usable. In the Corona meta-analysis, fresh sperm gave higher pregnancy rates (35% vs 20%), but the difference in live births was not confirmed. The trade-off with a fresh cycle is that, if no sperm are found, the eggs may need to be frozen instead.
Sources: AUA/ASRM — Diagnosis and Treatment of Infertility in Men: Guideline Part II; Transl Androl Urol (PMC) — Flannigan, Bach & Schlegel 2017, Microdissection testicular sperm extraction; Hum Reprod Update (PubMed) — Corona et al. 2019, Sperm recovery and ICSI outcomes in NOA; J Clin Med (PMC) — Colpi & Caroppo 2021, Performing microdissection TESE: surgical pearls
How micro TESE is performed, step by step
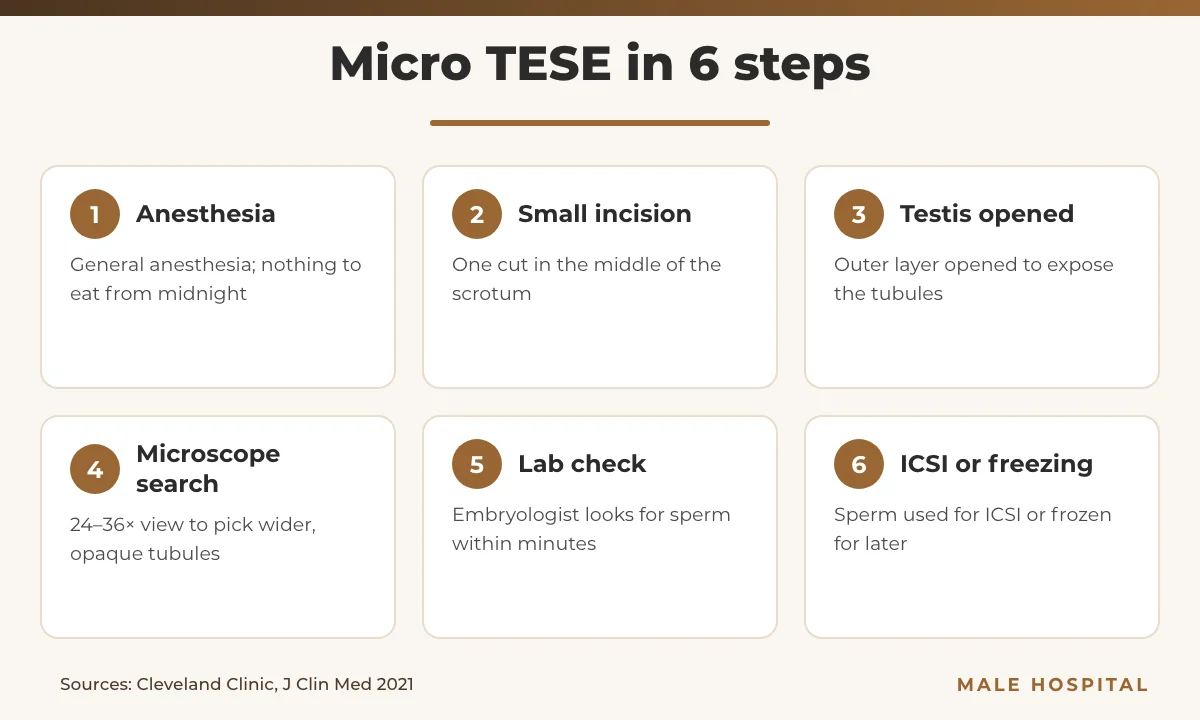
Exact micro TESE technique varies between surgeons, but the main steps are similar in published descriptions:
- Anesthesia: the operation is done under general anesthesia, so you are asleep. You will be asked not to eat or drink from midnight.
- Incision: a single small cut is made in the middle of the scrotum; one high-volume center describes 1.5–3 cm.
- Opening the testicle: the tough outer layer (tunica albuginea) is opened around its “equator” in an area without large blood vessels, exposing the tubules.
- Microscopic search: at 24–36× magnification the surgeon looks for dilated, opaque tubules and removes tiny samples. In one center’s series, dilated tubules contained sperm in about 90% of cases.
- Laboratory check: an embryologist or lab technologist minces and examines the tissue and reports within minutes whether sperm are present. If not, the search continues, and the other testicle may be explored.
- Closure and storage: the incisions are closed, and the sperm are used for ICSI or frozen.
Sources: Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction); J Clin Med (PMC) — Colpi & Caroppo 2021, Performing microdissection TESE: surgical pearls
Cleveland Clinic says micro TESE takes less than two hours. In the published series of one experienced Italian surgeon, the average time was 87 minutes for one testicle and 126 minutes when both were explored.
Sources: Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction); J Clin Med (PMC) — Colpi & Caroppo 2021, Performing microdissection TESE: surgical pearls
Micro TESE success rate and what predicts it

Cleveland Clinic states that healthy sperm can be retrieved in up to 60% of procedures, depending on the cause. Pooled data are a little lower: the Corona meta-analysis reported 47% per procedure across all TESE types in NOA. Results also differ widely between centers and improve with surgical experience.
Sources: Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction); Hum Reprod Update (PubMed) — Corona et al. 2019, Sperm recovery and ICSI outcomes in NOA; J Clin Med (PMC) — Colpi & Caroppo 2021, Performing microdissection TESE: surgical pearls
By testicular histology
The single strongest clue to micro TESE results is what the testicle tissue looks like under the microscope, which is often known only after surgery or from an earlier biopsy:
| Finding | What it means | Reported sperm retrieval |
|---|---|---|
| Hypospermatogenesis | All stages of sperm production present, but reduced | 73% or more |
| Late maturation arrest | Production stops at a late stage | 27–86% |
| Early maturation arrest | Production stops at an early stage | 27–40% |
| Sertoli-cell-only syndrome | Most tubules contain no sperm-making cells | 22.5–41% |
Sources: Transl Androl Urol (PMC) — Flannigan, Bach & Schlegel 2017, Microdissection testicular sperm extraction; EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
The microscope helps most when sperm production is patchy, as in Sertoli-cell-only syndrome; the EAU reports 22.5–41% with microdissection versus 6.3–29% with conventional TESE in this group. In maturation arrest, where all tubules look alike, there is no clear difference between techniques.
Sources: EAU — Sexual and Reproductive Health Guidelines (male infertility chapter); Andrology (PubMed) — Deruyver et al. 2014, Micro-TESE vs conventional TESE in NOA: a systematic review
Other predictors
No test can promise success before surgery. The EAU notes that FSH, LH, inhibin B, AMH and testicle volume correlate only inconsistently with the result, and that men with high FSH may still have small areas of sperm production. In the Corona analysis, retrieval did not depend on age or hormones, but a mean testis volume above 12.5 mL predicted retrieval rates above 60%.
Sources: EAU — Sexual and Reproductive Health Guidelines (male infertility chapter); Hum Reprod Update (PubMed) — Corona et al. 2019, Sperm recovery and ICSI outcomes in NOA
For Klinefelter syndrome, a separate meta-analysis of 37 studies and 1,248 men found sperm in 44% of TESE cycles, with similar results for microdissection and conventional TESE, and pregnancy and live birth rates of about 43% per ICSI cycle. None of the tested factors, including age, testicle size and hormones, predicted the outcome, although the EAU notes some evidence that younger men do better.
Sources: Hum Reprod Update (PubMed) — Corona et al. 2017, Sperm recovery and ICSI outcomes in Klinefelter syndrome; EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
Recovery after the operation
The NHS notes that surgical sperm extraction is usually an outpatient procedure, although some centers keep patients overnight to check for bleeding. According to Cleveland Clinic:
- The first one or two days after micro TESE are usually the most uncomfortable; ice packs and simple painkillers such as acetaminophen or anti-inflammatory drugs help.
- A few days off work are typical, longer for physically demanding jobs.
- Strenuous exercise and heavy lifting should be avoided for several days, and sex and masturbation for several days as well.
- Dissolvable stitches are often used, and most men recover fully within a few weeks.
Sources: NHS — Infertility: treatment; Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction); J Clin Med (PMC) — Colpi & Caroppo 2021, Performing microdissection TESE: surgical pearls
Recovery protocols after micro TESE differ. One high-volume center, for example, advises return to work at three days, sexual activity at ten days and intense exercise after twenty days, with oral antibiotics for about a week. Follow your own surgeon’s instructions.
Source: J Clin Med (PMC) — Colpi & Caroppo 2021, Performing microdissection TESE: surgical pearls
Risks, complications and testosterone
Cleveland Clinic lists the main risks of micro TESE as finding little or no sperm, reactions to anesthesia, bleeding, infection and pain. Permanent damage to the testicle is possible but very rare. Compared with conventional TESE, the EAU reports lower rates of hematoma and scarring after microdissection; after conventional TESE, 51.7% of men had an intratesticular hematoma on ultrasound at three months and up to 30% had fibrosis at six months.
Sources: Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction); EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
What happens to testosterone?
The testicle makes both sperm and testosterone, so removing tissue at micro TESE can lower hormone levels for a while. In data summarized by Flannigan, Bach and Schlegel, average testosterone fell from 316 to 251 ng/dL after surgery and returned to about 95% of baseline by 18 months. About 5–10% of men had a drop large enough to need testosterone replacement, and the AUA/ASRM guideline notes this remains a risk even with the microscopic technique. A follow-up hormone test, for example at 9 and 18 months, is reasonable, especially in men with Klinefelter syndrome or low levels before surgery.
Sources: Transl Androl Urol (PMC) — Flannigan, Bach & Schlegel 2017, Microdissection testicular sperm extraction; AUA/ASRM — Diagnosis and Treatment of Infertility in Men: Guideline Part II; J Clin Med (PMC) — Colpi & Caroppo 2021, Performing microdissection TESE: surgical pearls
After the result: ICSI, repeat surgery or donor sperm
If sperm are found
Retrieved sperm are always used with ICSI, because there are too few for natural conception or standard IVF. The UK regulator HFEA describes ICSI as the most common and successful treatment for male infertility. In the Corona meta-analysis of men with NOA, the live birth rate was about 24% per ICSI cycle, and it was not affected by the man’s age, testicle size or hormone levels; the female partner’s age and egg quality remain major factors. Extra sperm can be frozen for later cycles.
Sources: HFEA — Intracytoplasmic sperm injection (ICSI); Hum Reprod Update (PubMed) — Corona et al. 2019, Sperm recovery and ICSI outcomes in NOA
The HFEA also notes that a son conceived through ICSI may inherit his father’s infertility, which is highly likely when there is a known genetic cause on the Y chromosome. Genetic counselling before treatment helps couples make that decision with full information.
Source: HFEA — Intracytoplasmic sperm injection (ICSI)
If no sperm are found
A negative result is disappointing but not always final. The EAU reports that a salvage operation after a failed microdissection finds sperm in 18.4–42.8% of men, and after a failed conventional TESE or TESA, pooled success was 39.1%. Surgeons usually advise waiting 6–12 months before a repeat operation so the testicle can heal. Donor sperm and adoption are other paths. For the broader range of options, see our overview of male infertility.
Sources: EAU — Sexual and Reproductive Health Guidelines (male infertility chapter); Transl Androl Urol (PMC) — Flannigan, Bach & Schlegel 2017, Microdissection testicular sperm extraction; Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction)
When to see a doctor
Book a consultation with a urologist-andrologist if a semen test shows no sperm, if you have tried to conceive for 12 months without success, or if you had undescended testicles, chemotherapy or testicular surgery. After micro TESE, contact your surgeon promptly if you notice:
- Severe or worsening pain that painkillers do not control.
- Heavy bleeding from the incision or a rapidly growing scrotal swelling.
- Blood in the urine.
- Fever, chills, pus or spreading redness around the wound.
- Feeling very unwell, confused or breathless, which can be signs of sepsis and need emergency care.
Sources: Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction); EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
If you have been told you have azoospermia, you can arrange a confidential review with our urologist-andrologist Assoc. Prof. Dr. Zülfü Sertkaya, whose research includes micro TESE, male hormones and semen quality. Send your semen, hormone and genetic results by WhatsApp for a free first assessment.
FAQs about micro TESE
What is the success rate of micro TESE?
Across large studies of non-obstructive azoospermia, sperm are found in roughly 46–47% of procedures, and some centers report up to 60%. The chance depends mostly on the cause and the tissue pattern: it is highest with hypospermatogenesis and lowest with Sertoli-cell-only syndrome. Men with complete AZFa or AZFb deletions should not have surgery.
Sources: Hum Reprod Update (PubMed) — Corona et al. 2019, Sperm recovery and ICSI outcomes in NOA; Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction); EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
Can micro TESE be repeated?
Yes. If all retrieved sperm are used or none were found, a second micro TESE can be considered, usually after waiting 6–12 months for the testicle to recover. Published salvage rates after a failed microdissection range from about 18% to 43%, so repeat surgery is a realistic option for some men but not a certainty.
Sources: Transl Androl Urol (PMC) — Flannigan, Bach & Schlegel 2017, Microdissection testicular sperm extraction; EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
Does micro TESE lower testosterone?
It can, temporarily. In one large series, average testosterone fell from 316 to 251 ng/dL after surgery and returned to about 95% of baseline by 18 months. Around 5–10% of men needed testosterone replacement afterward. A follow-up blood test is advisable, and testosterone should only be started once no further fertility treatment is planned.
Sources: Transl Androl Urol (PMC) — Flannigan, Bach & Schlegel 2017, Microdissection testicular sperm extraction; AUA/ASRM — Diagnosis and Treatment of Infertility in Men: Guideline Part II
Is micro TESE better than TESA?
For non-obstructive azoospermia, the guidelines say yes. A randomized trial of 100 men reported sperm retrieval in 43% with microdissection versus 22% with multiple-pass TESA, and the EAU strongly recommends against needle methods in NOA. In obstructive azoospermia, where sperm production is normal, simpler needle methods usually work well.
Source: EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
Should micro TESE be done on the same day as egg collection?
Both approaches are accepted. The AUA/ASRM guideline says fresh or frozen testicular sperm may be used for ICSI. Fresh sperm may give higher pregnancy rates, but live birth differences have not been confirmed, and doing surgery first lets the couple know whether sperm exist before the partner starts ovarian stimulation.
Sources: AUA/ASRM — Diagnosis and Treatment of Infertility in Men: Guideline Part II; Hum Reprod Update (PubMed) — Corona et al. 2019, Sperm recovery and ICSI outcomes in NOA
How much does micro TESE cost?
The price depends on whether one or both testicles are explored, the anesthesia and hospital stay, sperm freezing, and the partner’s ICSI cycle. Insurance coverage varies and is often absent. A reliable estimate is only possible after your hormone, genetic and ultrasound results are reviewed, which you can arrange through a free WhatsApp consultation.
Source: Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction)
Medically reviewed by Assoc. Prof. Dr. Zülfü Sertkaya, urologist and andrologist (FEBU), Istanbul. Last reviewed: November 2026.
This article is for general information and does not replace an individual consultation with a qualified doctor.
- EAU — Sexual and Reproductive Health Guidelines (male infertility chapter)
- AUA/ASRM — Diagnosis and Treatment of Infertility in Men: Guideline Part II
- Cleveland Clinic — MicroTESE (Microdissection Testicular Sperm Extraction)
- J Clin Med (PMC) — Colpi & Caroppo 2021, Performing microdissection TESE: surgical pearls
- Transl Androl Urol (PMC) — Flannigan, Bach & Schlegel 2017, Microdissection testicular sperm extraction
- Hum Reprod (PubMed) — Schlegel 1999, Microdissection improves sperm yield with minimal tissue excision
- Hum Reprod Update (PubMed) — Corona et al. 2019, Sperm recovery and ICSI outcomes in NOA
- Hum Reprod Update (PubMed) — Corona et al. 2017, Sperm recovery and ICSI outcomes in Klinefelter syndrome
- Andrology (PubMed) — Deruyver et al. 2014, Micro-TESE vs conventional TESE in NOA: a systematic review
- NHS — Infertility: treatment
- HFEA — Intracytoplasmic sperm injection (ICSI)


