

Avanafil is a prescription PDE5 inhibitor for erectile dysfunction (ED), sold as Stendra in the United States and Spedra in Europe, in 50, 100 and 200 mg tablets. The usual starting dose is 100 mg taken about 15 to 30 minutes before sex, no more than once a day, and it only works with sexual stimulation. It is one of several first-line options in erectile dysfunction treatment; this guide focuses on what sets it apart from the other pills.
Sources: FDA — STENDRA prescribing information; EMA — Spedra summary of product characteristics
- Avanafil is the newest of the four widely approved PDE5 inhibitors (FDA 2012, EU 2013) and is labeled to be taken as early as about 15 minutes before sex.
- Start with 100 mg; the dose can go up to 200 mg or down to 50 mg, at most once a day. Food, especially a high-fat meal, can delay the effect.
- In a trial built to test fast onset, about 26–29% of attempts made roughly 15 minutes after a dose succeeded, versus about 15% on placebo.
- Headache, flushing, nasal congestion and back pain are the most common side effects. In network meta-analyses it looked less effective than sildenafil, tadalafil or vardenafil, although the EAU sees no proven difference between PDE5 inhibitors.
- Never take it with nitrates, “poppers”, riociguat/vericiguat or strong CYP3A4 inhibitors such as ketoconazole or ritonavir.
- What is avanafil (Stendra, Spedra) and how does it work?
- How fast does avanafil work, and how long does it last?
- Avanafil dosage: 50 mg, 100 mg and 200 mg
- Stendra vs Spedra: where the FDA and EMA labels differ
- How well avanafil works: clinical trial results
- Avanafil vs sildenafil, tadalafil and vardenafil
- Avanafil side effects
- Avanafil interactions and who should not take it
- When to see a doctor
- FAQs about avanafil
What is avanafil (Stendra, Spedra) and how does it work?
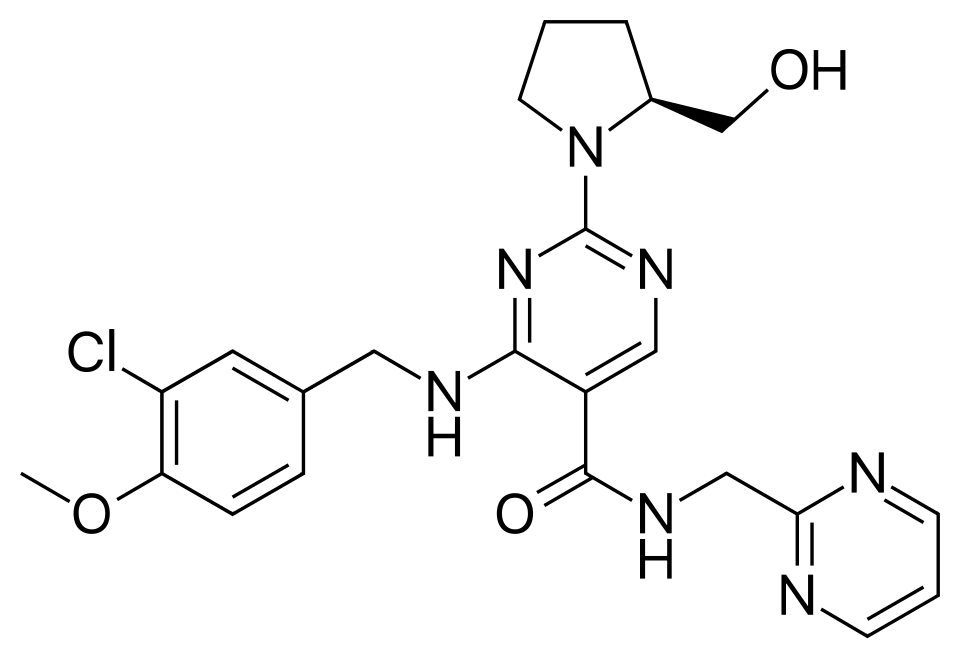
Avanafil is a phosphodiesterase type 5 (PDE5) inhibitor, the same drug class as sildenafil (Viagra), tadalafil (Cialis) and vardenafil (Levitra). The FDA first approved it in 2012 under the brand name Stendra, and the European Commission authorized it on 21 June 2013 as Spedra. Both labels have one indication: erectile dysfunction in adult men. It is not approved for women, for anyone under 18, or for men who do not have ED.
The tablets are oval and pale yellow, in 50 mg, 100 mg and 200 mg strengths. In the US, generic tablets are also marketed under an abbreviated new drug application and carry the same dosing and warnings as Stendra.
Sources: DailyMed — STENDRA label; EMA — Spedra EPAR; DailyMed — generic avanafil tablets label
The mechanism in plain terms
During sexual arousal, nerves in the penis release nitric oxide. This switches on an enzyme that makes a messenger molecule called cGMP, which relaxes the smooth muscle of the erectile tissue so blood can flow in. PDE5 is the enzyme that breaks cGMP down. By blocking PDE5, the drug lets cGMP build up and the erection becomes firmer and lasts longer. Because the process starts with nitric oxide released by arousal, the pill does nothing without sexual stimulation.
Laboratory studies show that it is highly selective for PDE5: it is more than 100 times more potent on PDE5 than on PDE6, the retinal enzyme linked to the “blue-tinted vision” side effect, and more than 10,000 times more potent than on PDE11. The EU label adds about 20,000-fold selectivity versus PDE3, an enzyme involved in heart muscle contraction. Selectivity in a test tube does not automatically mean fewer side effects in people, but it explains why visual disturbances were rare in trials.
Sources: FDA — STENDRA prescribing information; EMA — Spedra summary of product characteristics
Like every ED pill, it treats the symptom, not the cause. ED can be an early sign of blood vessel disease, diabetes or hormone problems, so both labels and the European Association of Urology (EAU) call for a medical history and examination before treatment. That assessment looks for treatable causes as well as risks.
Source: EAU Guidelines — Management of Erectile Dysfunction
How fast does avanafil work, and how long does it last?
Fast onset is avanafil’s main selling point. On an empty stomach it reaches peak blood levels in a median of 30 to 45 minutes, which is quicker than sildenafil or tadalafil. In a RigiScan study that measured penile rigidity, 200 mg produced erections firm enough for penetration in some men as early as 20 minutes after dosing.
The FDA label therefore allows the 100 mg and 200 mg doses to be taken “as early as approximately 15 minutes” before sex, while the 50 mg dose should be taken about 30 minutes before. The EU label gives a window of about 15 to 30 minutes for the recommended 100 mg dose. “As early as” is not “always by”: some men need longer, especially after a meal.
Sources: FDA — STENDRA prescribing information; EMA — Spedra summary of product characteristics
Food and timing
A high-fat meal slows absorption, delaying the peak by about 1.1 to 1.25 hours and cutting peak levels by 39%, though total exposure barely changes. The labels say the tablet may be taken with or without food, but the EU label warns that the onset may be delayed if taken with food. If speed matters to you, a light meal or an empty stomach gives the best chance of a quick response.
How long the effect lasts
The two regulators report different half-lives: about 5 hours in the US label and 6 to 17 hours in the EU label. Neither label states a fixed “window” of action, and the trials measured success over time rather than an exact duration. In practice, it is considered a short-acting, on-demand pill, closer to sildenafil than to tadalafil, whose effect can last up to 36 hours.
Sources: FDA — STENDRA prescribing information; EMA — Spedra summary of product characteristics; EAU Guidelines — Management of Erectile Dysfunction
Avanafil dosage: 50 mg, 100 mg and 200 mg

The recommended starting dose is 100 mg, taken as needed before sexual activity. Depending on how well it works and how well you tolerate it, your doctor may raise it to 200 mg or lower it to 50 mg. The label asks for the lowest dose that gives a good result, and the maximum frequency is once per day, whatever the strength.
In the year-long open-label extension study, everyone started on 100 mg and could ask to switch. About 75% of the men moved up to 200 mg, while fewer than 1% moved down to 50 mg, which suggests many men find the starting dose not quite enough.
Source: DailyMed — STENDRA label
Dose adjustments
- Alpha-blockers (for example tamsulosin or doxazosin for prostate symptoms): be stable on the alpha-blocker first, then start at 50 mg.
- Moderate CYP3A4 inhibitors (such as erythromycin, diltiazem, verapamil, fluconazole): the US maximum is 50 mg once in 24 hours.
- Strong CYP3A4 inhibitors (ketoconazole, itraconazole, ritonavir, clarithromycin and others): do not use it.
- Kidneys and liver: no change for mild to moderate impairment in the US label; do not use with severe kidney disease, dialysis or severe liver disease.
- Age 65 and over: no dose change is needed for age alone, though some older men are more sensitive to medicines.
Source: FDA — STENDRA prescribing information
Stendra vs Spedra: where the FDA and EMA labels differ
Stendra and Spedra contain the same drug in the same strengths, but the American and European regulators wrote their rules slightly differently. If you were prescribed the drug in one country and live in another, these differences are worth knowing.
| Topic | Stendra (FDA, US) | Spedra (EMA, EU) |
|---|---|---|
| Timing | 100/200 mg as early as ~15 min before sex; 50 mg ~30 min before | About 15–30 min before sex |
| Moderate CYP3A4 inhibitors | Max 50 mg, once every 24 hours | Max 100 mg, at least 48 hours between doses |
| Recent heart attack or stroke (6 months), uncontrolled blood pressure, unstable angina, heart failure NYHA class 2+ | Not recommended (not studied) | Contraindicated |
| Previous NAION (eye stroke) in one eye | Use with caution only if benefits outweigh risks | Contraindicated |
| Mild to moderate liver impairment | No dose adjustment | Start with the lowest effective dose |
| Grapefruit | Likely to raise blood levels | Avoid grapefruit juice within 24 hours before a dose |
| Terminal half-life | About 5 hours | About 6–17 hours |
Sources: FDA — STENDRA prescribing information; EMA — Spedra summary of product characteristics
The EU label also notes that men with mild or moderate kidney impairment responded less well in the phase 3 studies, and that side effects were more frequent in men with a body mass index under 25. Where the two labels differ, follow the one that applies where you were prescribed, and when in doubt, the stricter rule is the safer one.
Source: EMA — Spedra summary of product characteristics
How well avanafil works: clinical trial results
The drug was tested in four randomized, double-blind, placebo-controlled trials lasting two to three months. The main measures were the erectile function score of the International Index of Erectile Function (IIEF, 30 points maximum) and patient diaries recording whether penetration (SEP2) and successful intercourse (SEP3) happened.
| Trial population | Placebo | 100 mg | 200 mg |
|---|---|---|---|
| General ED (646 men): successful intercourse at end of study | 27.0% | 57.1% | 57.0% |
| ED with diabetes (390 men) | 20.5% | 34.4% | 40.0% |
| After nerve-sparing radical prostatectomy (286 men) | 8.9% | 23.4% | 26.4% |
| Onset study (440 men): success when attempting ~15 min after dosing (mean) | 14.9% | 25.9% | 29.1% |
Source: DailyMed — STENDRA label
In the general ED trial, the 50 mg dose raised the IIEF erectile function score by 5.4 points, 100 mg by 8.3 and 200 mg by 9.5, compared with 2.9 on placebo. All differences were statistically significant. Results were smaller, as with every PDE5 inhibitor, in men with diabetes and after prostate cancer surgery, groups whose nerves and blood vessels are often damaged.
Keep the onset numbers in perspective. Attempting sex 15 minutes after a dose worked in roughly one in four attempts, compared with about one in seven on placebo. The drug can work quickly, but most men will do better giving it a little more time.
Sources: FDA — STENDRA prescribing information; EMA — Spedra EPAR
Avanafil vs sildenafil, tadalafil and vardenafil
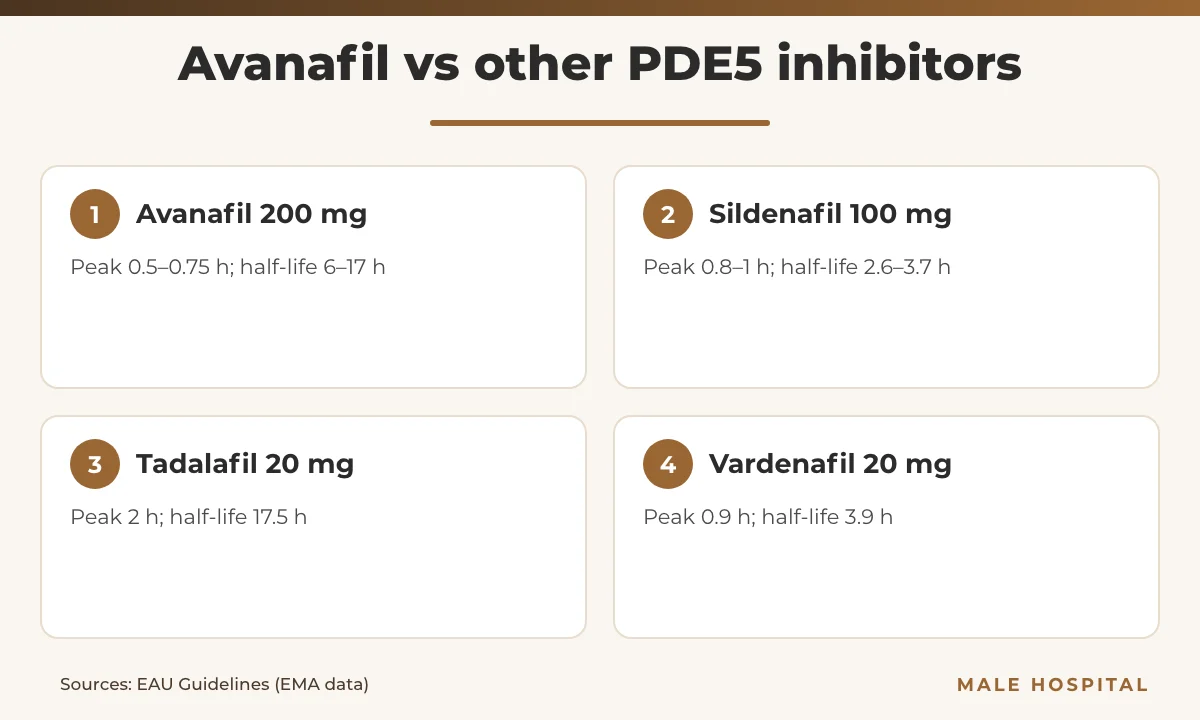
No large head-to-head trial has compared it directly with the other pills, so comparisons rely on regulatory data and network meta-analyses that combine many placebo-controlled trials. The table below uses figures from the EAU guidelines, which take their pharmacokinetic and side-effect data from the European product labels at the highest recommended dose.
| Feature | Avanafil 200 mg | Sildenafil 100 mg | Tadalafil 20 mg | Vardenafil 20 mg |
|---|---|---|---|---|
| Time to peak level | 0.5–0.75 h | 0.8–1 h | 2 h | 0.9 h |
| Half-life | 6–17 h | 2.6–3.7 h | 17.5 h | 3.9 h |
| Delayed by a high-fat meal | Yes | Yes | No mention | Yes |
| Headache | 9.3% | 12.8% | 14.5% | 16% |
| Flushing | 3.7% | 10.4% | 4.1% | 12% |
| Nasal congestion | 1.9% | 1.1% | 4.3% | 10% |
| Abnormal vision | None | 1.9% | Not listed | <2% |
Source: EAU Guidelines — Management of Erectile Dysfunction
Is avanafil as effective as the others?
The evidence is mixed. A 2013 network meta-analysis of 118 trials (31,195 men) found avanafil less effective than tadalafil and vardenafil on a global “did the treatment improve your erections?” question, with no major safety differences between drugs. A 2015 trade-off analysis of 82 trials found that, at starting doses, avanafil 100 mg had a similar overall side-effect rate to sildenafil 50 mg but markedly lower global efficacy. It had fewer trials than the older drugs, which widens the uncertainty.
Sources: European Urology — Yuan et al. 2013 network meta-analysis; European Urology — Chen et al. 2015 trade-off network meta-analysis; Australian Prescriber — Avanafil for erectile dysfunction
The EAU guidelines nevertheless conclude that there is no demonstrated difference in efficacy between the PDE5 inhibitors, and that the choice should depend on how often you have sex and your own experience with the drugs. In practice, avanafil suits men who want a quick-acting, on-demand pill with a relatively low rate of flushing and visual effects. Men who want spontaneity over a whole weekend often prefer tadalafil (see our Viagra vs Cialis comparison), and our vardenafil guide covers the other short-acting option.
Source: EAU Guidelines — Management of Erectile Dysfunction
Avanafil side effects
Most side effects are mild and come from the same blood vessel-widening action that helps erections. In three placebo-controlled US trials of up to three months, the most common were:
- Headache: 5.1% at 50 mg, 6.9% at 100 mg and 10.5% at 200 mg, versus 1.7% on placebo.
- Flushing: 3.2–4.3% across doses, versus 0% on placebo.
- Nasal congestion: 1.8–2.9%, versus 1.1% on placebo.
- Back pain: 1.1–3.2%, versus 1.1% on placebo.
- Nasopharyngitis (cold-like symptoms) was also listed, at rates close to placebo.
Only 1.4–2.0% of men stopped treatment because of side effects, compared with 1.7% on placebo. Across all trials, a single participant reported a change in color vision. Less common effects included dizziness, indigestion, nausea and rash.
Source: DailyMed — STENDRA label
Rare but serious effects
Like every PDE5 inhibitor, it carries class warnings for an erection lasting more than 4 hours (priapism), sudden loss of vision in one or both eyes, which may be non-arteritic anterior ischemic optic neuropathy (NAION), and sudden decrease or loss of hearing, sometimes with ringing in the ears or dizziness. No cases of NAION, sudden hearing loss or priapism were reported in avanafil’s own clinical trials, but the risk is assumed for the whole class. Allergic reactions with itching or eyelid swelling have also been reported.
Sources: EMA — Spedra summary of product characteristics; MedlinePlus — Avanafil
The drug did not harm sperm: in a 26-week study of daily 100 mg doses in healthy men, sperm count, motility, shape and semen volume were unaffected. For comparison with the older pills, see our article on sildenafil side effects.
Source: FDA — STENDRA prescribing information
Avanafil interactions and who should not take it
Never combine with
- Nitrates in any form (nitroglycerin, isosorbide mononitrate or dinitrate) and nitrite “poppers”: the combination can drop blood pressure to dangerous levels. If nitrates are needed in an emergency, at least 12 hours should pass after the last dose, and only under medical monitoring.
- Guanylate cyclase stimulators riociguat and vericiguat, used for pulmonary hypertension and heart failure.
- Strong CYP3A4 inhibitors such as ketoconazole, itraconazole, ritonavir and other HIV protease inhibitors, clarithromycin, nefazodone and telithromycin. Ketoconazole raised blood levels about 13-fold.
- Other ED treatments, including another PDE5 inhibitor: the combination has not been studied and is not recommended. Our article on taking Viagra and Cialis together explains the general risk.
Source: FDA — STENDRA prescribing information
Use with care
Alpha-blockers and other blood pressure drugs add to its mild blood pressure-lowering effect; a 200 mg dose lowered seated blood pressure by about 8/3 mmHg in healthy volunteers. More than 3 units of alcohol can increase dizziness, fast heartbeat, headache and a drop in standing blood pressure. Grapefruit juice and moderate CYP3A4 inhibitors raise its levels, and enzyme inducers such as rifampicin or carbamazepine may reduce its effect, so that combination is not recommended.
Sources: DailyMed — STENDRA label; EMA — Spedra summary of product characteristics
Who should avoid or be cautious
Avanafil should not be used by men for whom sex is inadvisable because of heart disease, or by those with a heart attack, stroke or life-threatening arrhythmia in the past 6 months, blood pressure below 90/50 or above 170/100 mmHg, unstable angina or significant heart failure. It is also avoided in severe kidney or liver disease and hereditary retinal disorders such as retinitis pigmentosa. Extra caution applies with Peyronie’s disease or other penile deformity, conditions that predispose to priapism (sickle cell anemia, multiple myeloma, leukemia), bleeding disorders and active stomach ulcers. If you have heart disease, read our guide on erectile dysfunction and heart disease first.
Sources: FDA — STENDRA prescribing information; Cleveland Clinic — Phosphodiesterase Inhibitors
When to see a doctor
Get emergency help, and say that you took avanafil and when, if you have:
- An erection lasting more than 4 hours, painful or not.
- Chest pain, dizziness or nausea during sex. Do not take nitroglycerin on your own; tell the emergency team about avanafil.
- Sudden loss of vision in one or both eyes, or sudden loss of hearing.
- Fainting, severe lightheadedness, or swelling of the face or eyelids.
Book a routine visit if the pill has not worked after several attempts at the right dose and timing, if side effects bother you, or before starting any new medicine, especially antifungals, antibiotics, HIV drugs or blood pressure tablets. New ED in an otherwise healthy man also deserves a check, because it can come before heart disease or diabetes is diagnosed.
Sources: MedlinePlus — Avanafil; Cleveland Clinic — Phosphodiesterase Inhibitors
If you are unsure whether avanafil or another pill suits you, or if tablets have stopped working, you can arrange a confidential consultation with our urologist-andrologist via WhatsApp. We will review your health and medicines and explain every erectile dysfunction treatment option, from tablets to injections and implants.
FAQs about avanafil
Is avanafil better than Viagra?
Not clearly. It reaches peak levels faster and caused less flushing and fewer visual effects in label data, but network meta-analyses suggest it is somewhat less effective than sildenafil at starting doses. The EAU says no difference in efficacy between PDE5 inhibitors has been proven. Which works better depends on the individual, so some men try more than one under medical supervision.
Sources: European Urology — Chen et al. 2015; EAU Guidelines — Management of Erectile Dysfunction
How long before sex should I take avanafil?
The US label allows 100 mg or 200 mg to be taken as early as about 15 minutes before sex, and 50 mg about 30 minutes before. The European label suggests 15 to 30 minutes. Some men need longer, especially after a large or fatty meal, so many find it easier to take it a little earlier rather than rely on the minimum time.
Source: MedlinePlus — Avanafil
Can I drink alcohol with avanafil?
Small amounts are generally acceptable, but heavy drinking is not. The FDA label warns that more than about 3 units of alcohol with avanafil can raise heart rate, lower standing blood pressure and cause dizziness and headache.
Source: FDA — STENDRA prescribing information
Can I take avanafil every day?
Avanafil is approved only for on-demand use, at most once a day. In a safety study, healthy men took 100 mg daily for 26 weeks without effects on sperm, but there is no approved daily-dose regimen for ED. Men who want continuous daily treatment usually discuss low-dose daily tadalafil with their doctor instead.
Source: FDA — STENDRA prescribing information
Can I take 300 mg of avanafil if 200 mg does not work?
No. The maximum recommended dose is 200 mg, once a day. Higher doses were given only in research settings, and side effects rose with dose: headache, for example, increased from about 5% at 50 mg to 10.5% at 200 mg. If 200 mg taken correctly fails, ask your doctor about another PDE5 inhibitor or second-line options such as penile injections.
Source: DailyMed — STENDRA label
Does avanafil work after prostate surgery?
It can help some men. In a trial of men who had nerve-sparing radical prostatectomy, successful intercourse at the end of the study was 23.4% on 100 mg and 26.4% on 200 mg, compared with 8.9% on placebo. Results after surgery are lower than in the general ED population, because nerve recovery takes time.
Source: DailyMed — STENDRA label
Is Spedra the same as Stendra?
Yes, both contain avanafil in 50, 100 and 200 mg tablets. Spedra is the European brand and Stendra the US brand. The labels differ in some details: for example, the EU label contraindicates use after recent heart attack or stroke and after NAION, and allows up to 100 mg every 48 hours with moderate CYP3A4 inhibitors, while the US label caps that at 50 mg per 24 hours.
Source: EMA — Spedra EPAR
Medically reviewed by Assoc. Prof. Dr. Zülfü Sertkaya, urologist and andrologist (FEBU), Istanbul. Last reviewed: November 2026.
This article is for general information and does not replace an individual consultation with a qualified doctor.
- FDA — STENDRA (avanafil) tablets — prescribing information (revised 10/2022)
- DailyMed (NLM) — STENDRA (avanafil) tablet — label
- DailyMed (NLM) — Avanafil tablets (generic) — label
- European Medicines Agency — Spedra (avanafil) — summary of product characteristics
- European Medicines Agency — Spedra — European public assessment report (EPAR)
- EAU — Sexual and Reproductive Health Guidelines — Management of Erectile Dysfunction
- MedlinePlus — Avanafil
- Cleveland Clinic — Phosphodiesterase Inhibitors
- Australian Prescriber (PMC) — Avanafil for erectile dysfunction (2019)
- European Urology (PubMed) — Comparative effectiveness and safety of oral PDE5 inhibitors for ED: network meta-analysis (Yuan et al., 2013)
- European Urology (PubMed) — PDE5 inhibitors for the treatment of ED: a trade-off network meta-analysis (Chen et al., 2015)


