

Psychological erectile dysfunction (also called psychogenic ED) is difficulty getting or keeping an erection that is driven mainly by the mind rather than by blood vessels, nerves or hormones, with common triggers being performance anxiety, stress, depression and relationship problems. It is real, common and very treatable, but most men with ED have a mix of physical and psychological factors, so a medical check comes first. Treatment usually combines talking therapy, such as cognitive behavioral therapy (CBT) or sex therapy, with medicine when needed.
Source: EAU Guidelines — Management of erectile dysfunction; NIDDK — Symptoms & Causes of ED
- European urology guidelines classify ED as organic, psychogenic or mixed, but warn that most cases are of mixed cause.
- Performance anxiety, stress, depression, relationship conflict and trauma are the best-documented psychological triggers. Research does not show that ordinary pornography use causes ED.
- Normal morning or night-time erections and sudden, situational problems point toward a psychological cause, but they do not rule out a physical one.
- CBT, ideally with the partner involved and combined with medical treatment, is a strong recommendation in the EAU guidelines.
- Pills such as sildenafil or tadalafil can help break the anxiety cycle, and they also help men whose ED is caused by antidepressants.
- What is psychological erectile dysfunction?
- Common triggers of psychological erectile dysfunction
- Does pornography cause erectile dysfunction?
- Mind and body: why most ED is mixed
- Clues that ED may be psychological
- How doctors assess psychological ED
- Psychological erectile dysfunction treatment
- Self-help steps that support recovery
- When to see a doctor
- FAQs about psychological erectile dysfunction
What is psychological erectile dysfunction?
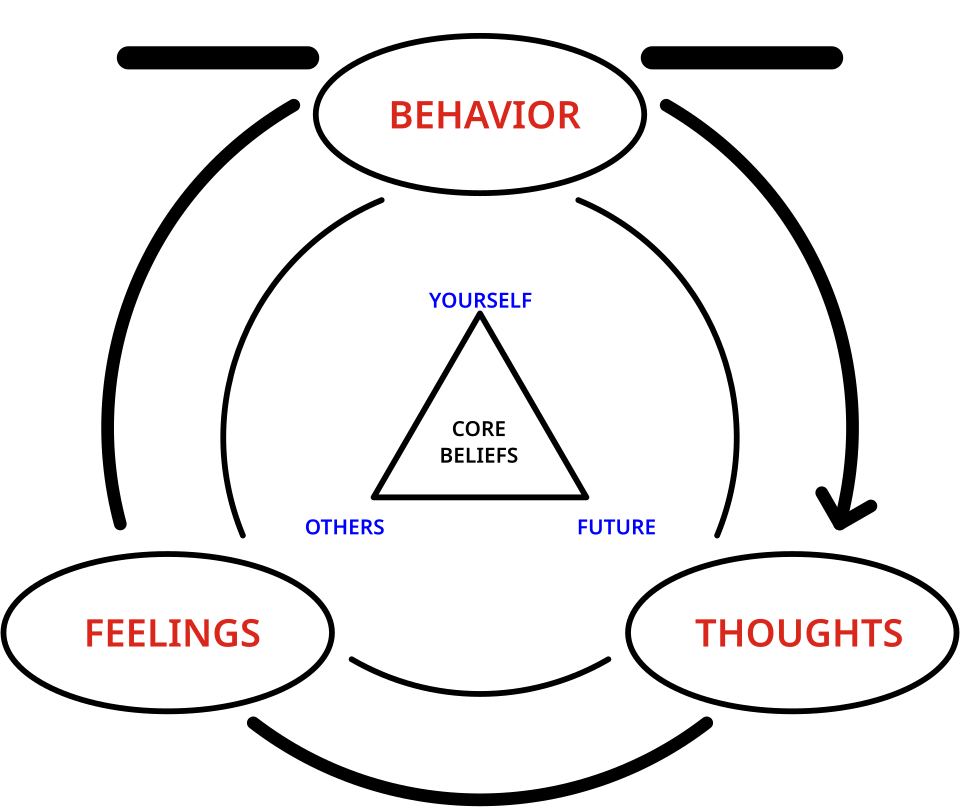
An erection is not just a plumbing event. It starts in the brain: sexual thoughts and touch send nerve signals that relax the smooth muscle of the penis and let blood flow in. When the mind is flooded with worry, fear or low mood, those signals can be blocked even when the blood vessels and nerves are perfectly healthy. That is the core idea behind psychological erectile dysfunction.
The European Association of Urology (EAU) groups erectile dysfunction (ED) into three types by cause: organic (physical), psychogenic (psychological) and mixed. It divides psychogenic ED into a generalized type, such as a general lack of arousal or problems with sexual intimacy, and a situational type, linked to a particular partner, to performance worries or to distress. The guideline adds a caution: this classification should be used carefully, because most cases have mixed causes.
Source: EAU Guidelines — Management of erectile dysfunction
Doctors also separate primary ED (a man has never been able to have reliable erections) from secondary ED (problems after a period of normal function). The MSD Manual notes that psychological causes of primary ED include guilt, fear of intimacy, depression or anxiety, while in secondary ED performance anxiety, stress and depression are typical. It also stresses that psychological factors must be considered in every case of ED, whatever the main cause.
Source: MSD Manual Professional — Erectile Dysfunction
Psychological ED is not “all in your head” in the sense of being imagined. The erection problem is real and measurable, and it deserves the same respectful assessment as any other health issue. For a full overview of the condition, see our guide to erectile dysfunction.
Common triggers of psychological erectile dysfunction

The U.S. National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) lists anxiety, depression, stress, feeling isolated or lonely, low self-esteem, lack of confidence and negative body image as mental or emotional issues that can either cause ED or make it worse. The main triggers are described below.
Source: NIDDK — Symptoms & Causes of ED
Performance anxiety
Performance anxiety is the classic driver of situational ED. One disappointing erection, perhaps after alcohol, tiredness or a new partner, leads to worry that it will happen again. During the next encounter the man is watching his penis instead of enjoying the moment, which is called “spectatoring.” Distraction and worry get in the way of arousal, and the erection fades. That failure seems to confirm the fear, and a self-reinforcing cycle begins. The EAU guideline lists performance-related issues and distress among the situational causes of psychogenic ED.
Stress and tiredness
The NHS notes that occasional erection problems are usually caused by stress, tiredness or drinking too much alcohol. Work pressure, money worries, caring duties and poor sleep all reduce the mental space needed for arousal. Short episodes like these are common and usually pass.
Source: NHS — Erection problems (erectile dysfunction); EAU Guidelines — Management of erectile dysfunction
Depression
Depression and ED are closely linked in both directions. A 2018 meta-analysis of 49 publications in the Journal of Sexual Medicine found that depression was associated with higher odds of ED (pooled odds ratio 1.39), and that men with ED had almost three times the odds of developing depression (odds ratio 2.92). The authors could not prove which comes first, and they recommended that men with ED be screened for depression and that men with depression be asked about erections.
Relationship conflict
Unresolved anger, poor communication, fear of rejection or pressure to conceive can all make sex feel like a test. The EAU guideline notes that relationship factors are linked to erectile difficulties and that intimacy appears to protect against ED. This is one reason guidelines encourage involving the partner in treatment.
Source: EAU Guidelines — Management of erectile dysfunction
Trauma and PTSD
Past sexual trauma, combat experience and other traumatic events can affect sexual function. In a study of 405,275 male U.S. veterans of the Iraq and Afghanistan wars, those with post-traumatic stress disorder (PTSD) had more than three times the risk of sexual dysfunction after adjustment for other factors. The risk was highest when psychiatric medicines were also prescribed, but PTSD raised the risk even without them.
Does pornography cause erectile dysfunction? What the evidence shows
The idea of “porn-induced ED” is widely discussed online, so it is worth looking at the evidence carefully. A 2016 review with clinical case reports proposed that heavy internet pornography use might condition arousal to novelty and screen content, so that partnered sex feels less arousing. The authors described men who improved after stopping, but they presented this as a hypothesis that needs proper research, not as proven fact.
Larger surveys have not found a clear link. A study of about 3,900 men from Croatia, Norway and Portugal found little evidence that pornography use was associated with erectile, desire or orgasm problems in younger men. A 2019 study that followed men over a year found no consistent link between simply using pornography and ED. However, men who felt their own use was problematic did report more erectile difficulties at the same time, with no evidence that either caused the other.
Source: PubMed — Landripet & Štulhofer, Pornography use and sexual difficulties in younger men (J Sex Med 2015); PubMed — Grubbs & Gola, Is pornography use related to erectile functioning? (J Sex Med 2019)
The balanced take: current evidence does not show that ordinary pornography use causes ED. If your use feels compulsive, causes guilt or conflict, or seems tied to your erection problems, that is still worth discussing with a doctor or therapist. Shame and conflict can feed performance anxiety whatever the cause.
Mind and body: why most psychological erectile dysfunction is mixed
Pure psychological ED and pure physical ED are the two ends of a spectrum, and most men are somewhere in between. A man whose erections are weakening because of narrowed arteries or diabetes soon starts to worry before sex, and that worry makes the erection even less reliable. The MSD Manual notes that many men with secondary ED develop reactive psychological difficulties that add to the original problem.
The reverse also happens. Depression is linked to ED, and so are the medicines used to treat it: NIDDK lists antidepressants among the common medicines that can cause ED, and the EAU names selective serotonin reuptake inhibitors (SSRIs) and tricyclic antidepressants as drug causes. Learn more about the full range of erectile dysfunction causes, including vascular, hormonal and nerve causes.
Source: MSD Manual Professional — Erectile Dysfunction; NIDDK — Symptoms & Causes of ED; EAU Guidelines — Management of erectile dysfunction
This matters: labeling ED “just psychological” can delay diagnosis of diabetes or heart disease, while labeling it “just physical” can leave the anxiety untreated.
Clues that ED may be psychological (and their limits)

Some features of the history point toward a psychological cause. The MSD Manual says a psychological cause should be suspected in young, healthy men whose ED starts abruptly, when the problem began after an emotional event, when it happens only in certain situations, places or with certain partners, and when it improves on its own. Men with psychogenic ED usually have normal erections during sleep and on waking.
Source: MSD Manual Professional — Erectile Dysfunction
| Feature | Suggests psychological | Suggests physical |
|---|---|---|
| Onset | Sudden, often after a stressful event | Gradual over months or years |
| Pattern | Only with a partner or in certain settings | In all situations and with all partners |
| Night and morning erections | Usually present and firm | Often reduced or absent |
| Course | Comes and goes, may improve on its own | Steadily worsens |
| Age and health | Younger man without risk factors | Diabetes, heart disease, smoking, older age |
Source: MSD Manual Professional — Erectile Dysfunction; EAU Guidelines — Management of erectile dysfunction
Treat these clues as signposts, not a diagnosis. Morning erections can be present in early vascular ED, and a stressful life event can coincide with the start of a physical illness. Self-diagnosis also risks missing an early warning sign of heart disease, so a medical review is still worthwhile even when the story sounds psychological.
How doctors assess psychological ED
A good assessment looks at the body and the mind together. The doctor takes a medical and sexual history, reviews medicines, examines you and usually orders blood tests such as glucose, lipids and, when indicated, testosterone. Questionnaires such as the International Index of Erectile Function (IIEF) help measure severity.
The EAU guideline strongly recommends that the sexual history consider psychosexual development, life stressors, cultural aspects and cognitive factors. It notes that depression and anxiety disorders are frequently present alongside ED, that relationship factors and dysfunctional beliefs about sex should be explored, and that assessment should be adapted for gay, bisexual and other sexual-minority men.
Source: EAU Guidelines — Management of erectile dysfunction
When the cause remains unclear, nocturnal penile tumescence and rigidity (NPTR) testing records erections during sleep. Men with psychogenic ED usually have normal results, which helps separate psychological from physical ED. The EAU notes limits, however: depression and other factors can affect the result, which restricts its routine use for diagnosis.
Source: EAU Guidelines — Management of erectile dysfunction; MSD Manual Professional — Erectile Dysfunction
Psychological erectile dysfunction treatment: what works
The MSD Manual states that sex therapy should be the mainstay of treatment for men with psychogenic ED, and that reassurance and education, including for the partner whenever possible, are important for all patients. In practice, most men do best with a plan that combines psychological and medical tools.
Source: MSD Manual Professional — Erectile Dysfunction
Cognitive behavioral therapy (CBT)
CBT helps you notice and challenge unhelpful thoughts (“I will fail again,” “a real man is always ready”) and gradually change avoidance behavior. The EAU guideline gives a strong recommendation to direct patients to CBT as a psychological approach, including the partner, combined with medical treatment. It notes that CBT works in group or couple formats, even online, and that combining CBT with medication for ED has shown real efficacy and is considered best practice.
Source: EAU Guidelines — Management of erectile dysfunction
Sex therapy and sensate focus
A sex therapist is a licensed professional who works on the mental and emotional side of sexual problems through talk therapy and private homework exercises. Sessions involve no physical contact or sexual activity with the therapist, and you can attend alone or with your partner. Because sex therapists do not treat physical conditions, a medical evaluation is often done first.
Source: Cleveland Clinic — Sex Therapist: What They Do and When To See One
A common sex therapy tool is sensate focus, developed by Masters and Johnson. Partners take turns touching each other, starting with non-sexual touch and moving to sexual touch, while focusing on sensation instead of performance, and they talk openly about feelings and boundaries. The aim is to take pressure off erections, which can help with performance anxiety and ED.
Source: ISSM — What Is the Sensate Focus Technique?
Couples and group therapy
A Cochrane review of 11 trials (398 men) found that group psychotherapy reduced the number of men with persistent ED compared with no treatment, and focused sex-group therapy worked especially well. Men who received group therapy plus sildenafil did better than men on sildenafil alone and were less likely to drop out. The trials were small and old, so the evidence is limited, but it supports psychological treatment. The EAU guideline also lists marital therapy, sexual skills training and psychosexual education among psychosocial options.
Source: PubMed — Melnik et al., Psychosocial interventions for erectile dysfunction (Cochrane 2007); EAU Guidelines — Management of erectile dysfunction
Mindfulness-based therapy
Mindfulness teaches non-judgmental attention to the present moment, which directly counters spectatoring. A 2018 pilot study of 10 men with situational ED found a four-week mindfulness group was feasible and showed promising improvements in erectile function and sexual satisfaction. It had no control group, so mindfulness for ED should be seen as promising but not yet proven.
Source: PubMed — Bossio et al., Mindfulness-based group therapy for men with situational ED (J Sex Med 2018)
PDE5 inhibitors to break the anxiety cycle
Tablets such as sildenafil (Viagra) and tadalafil (Cialis) are phosphodiesterase type 5 (PDE5) inhibitors. They do not create desire, but they make an erection easier when you are aroused. For a man caught in the anxiety cycle, a few successful experiences can rebuild confidence, and the medicine can later be reduced or stopped if erections return reliably. This is why the EAU sees combined CBT and medication as best practice, and why the Cochrane review found group therapy plus sildenafil better than sildenafil alone. Compare the options in Viagra vs Cialis and check possible sildenafil side effects before starting. PDE5 inhibitors must never be taken with nitrate heart medicines.
Source: EAU Guidelines — Management of erectile dysfunction; PubMed — Melnik et al., Psychosocial interventions for ED (Cochrane 2007)
Treating depression and antidepressant-related ED
If depression is present, treating it matters for its own sake and may help sexual function. When an antidepressant itself seems to cause ED, a Cochrane review of 23 trials found that adding sildenafil or tadalafil improved erectile function in men compared with placebo. Evidence for switching antidepressants or taking “drug holidays” was lacking. Never stop or change an antidepressant on your own: discuss sexual side effects openly with your prescriber.
Source: PubMed — Taylor et al., Strategies for managing sexual dysfunction induced by antidepressant medication (Cochrane 2013); PubMed — Liu et al., ED and depression meta-analysis (J Sex Med 2018)
Self-help steps that support recovery
Self-help works best alongside, not instead of, a medical check. These steps are low-risk and fit with the approaches above:
- Talk to your partner. Explaining that the problem is common and treatable lowers pressure on both of you. Partner education is part of standard care.
- Take intercourse off the table for a while. Agreeing to touch, kiss and explore without aiming for penetration is the logic behind sensate focus.
- Reduce stress and alcohol. The NHS lists reducing stress and anxiety among helpful lifestyle changes, and links occasional ED to stress, tiredness and alcohol.
- Look after your mood and sleep. If you feel low most days or have lost interest in things you used to enjoy, speak to a doctor. Depression is treatable.
- Challenge “all or nothing” thinking. One soft erection is not a verdict on your masculinity or your relationship.
- Find a qualified therapist. The NHS advises choosing a sex therapist registered with a recognized professional body.
Source: NHS — Erection problems (erectile dysfunction); ISSM — What Is the Sensate Focus Technique?; MSD Manual Professional — Erectile Dysfunction
When to see a doctor about psychological erectile dysfunction
The NHS advises seeing a doctor or sexual health clinic if erection problems keep happening, because they can be a sign of a treatable health condition. Seek medical advice promptly if:
- ED lasts more than a few weeks or keeps coming back.
- You also have chest pain, shortness of breath on exertion, high blood pressure, diabetes or a strong family history of heart disease.
- Morning erections have disappeared, or ED is getting steadily worse in every situation.
- You notice low sex drive, fatigue or loss of body hair, which may point to a hormone problem.
- ED started after a new medicine, or you are on antidepressants and sexual side effects are making you think about stopping them.
- You feel hopeless, very anxious or have thoughts of self-harm. Contact a doctor or emergency services right away.
Source: NHS — Erection problems (erectile dysfunction); NIDDK — Symptoms & Causes of ED
If you would like a confidential assessment of both the physical and psychological sides of your erection problems, our urologist-andrologist can review your situation and explain your erectile dysfunction treatment options. You can start with a free, private consultation on WhatsApp.
FAQs about psychological erectile dysfunction
Can psychological erectile dysfunction be cured?
Often, yes. Psychological ED has a good outlook because the blood vessels and nerves usually work normally. In a Cochrane review, focused group sex therapy helped most men compared with no treatment. CBT, sex therapy and, when needed, a short course of a PDE5 inhibitor can restore confidence. Some men have relapses during stressful periods, which usually respond to the same tools.
Source: PubMed — Melnik et al., Psychosocial interventions for ED (Cochrane 2007)
How do I know if my ED is psychological or physical?
Clues toward a psychological cause include sudden onset, problems only with a partner or in certain situations, and normal erections during sleep or on waking. Gradual worsening in all situations points to a physical cause. Because most cases are mixed and ED can be an early sign of heart disease, a doctor should still check blood pressure, blood sugar and cholesterol.
Source: MSD Manual Professional — Erectile Dysfunction
Does Viagra work for psychological ED?
PDE5 inhibitors such as sildenafil can help men with psychological ED because they make erections easier once arousal starts, which can break the cycle of anxiety and failure. The EAU considers combining CBT with medication best practice, and a Cochrane review found group therapy plus sildenafil worked better than sildenafil alone. A doctor should confirm the medicine is safe for you first.
Source: EAU Guidelines — Management of erectile dysfunction
Can anxiety alone cause erectile dysfunction?
Yes. Anxiety is one of the mental health issues NIDDK lists as able to cause ED or make it worse, and performance-related worry is a recognized type of situational psychogenic ED in the EAU guideline. Even so, a medical check is sensible before assuming anxiety is the only cause.
Source: NIDDK — Symptoms & Causes of ED; EAU Guidelines — Management of erectile dysfunction
Can antidepressants cause erectile dysfunction?
Yes. NIDDK lists antidepressants among common medicines that can cause ED, and the EAU names SSRIs and tricyclic antidepressants. Depression itself is also linked to ED. For men with antidepressant-related ED, a Cochrane review found that adding sildenafil or tadalafil improved erections. Do not stop your antidepressant without talking to the doctor who prescribed it.
Source: PubMed — Taylor et al., Managing antidepressant-induced sexual dysfunction (Cochrane 2013)
Is “porn-induced ED” real?
It is debated. Some clinicians report men whose erections improved after they stopped heavy internet pornography use, but large surveys and a one-year follow-up study found no consistent link between pornography use and ED. Men who see their own use as problematic do report more erection problems, without proof of cause. If your use troubles you, a therapist can help.
Source: PubMed — Grubbs & Gola, Pornography use and erectile functioning (J Sex Med 2019)
Should my partner come to therapy?
It often helps. The EAU guideline recommends including the partner when directing men to CBT, and notes that intimacy appears to protect against ED. Sex therapy can be done alone or as a couple, and exercises such as sensate focus are designed for partners. If your partner cannot attend, individual therapy is still worthwhile.
Source: EAU Guidelines — Management of erectile dysfunction; Cleveland Clinic — Sex Therapist
How long does treatment for psychological ED take?
It varies with the cause and the person. The mindfulness program studied for situational ED ran for four weeks, while deeper issues such as trauma or relationship conflict may need longer work. No single timeline fits everyone, so agree on goals and review progress with your therapist or doctor.
Source: PubMed — Bossio et al., Mindfulness-based group therapy for situational ED (J Sex Med 2018)
Medically reviewed by Assoc. Prof. Dr. Zülfü Sertkaya, urologist and andrologist (FEBU), Istanbul. Last reviewed: October 2026.
This article is for general information and does not replace an individual consultation with a qualified doctor.
- EAU — Sexual and Reproductive Health Guidelines — Management of erectile dysfunction
- NIDDK — Symptoms & Causes of Erectile Dysfunction
- NHS — Erection problems (erectile dysfunction)
- MSD Manual Professional — Erectile Dysfunction
- Cleveland Clinic — Sex Therapist: What They Do and When To See One
- ISSM — What Is the Sensate Focus Technique?
- PubMed — Cochrane Database Syst Rev 2007 — Melnik et al. Psychosocial interventions for erectile dysfunction
- PubMed — Cochrane Database Syst Rev 2013 — Taylor et al. Strategies for managing sexual dysfunction induced by antidepressant medication
- PubMed — J Sex Med 2018 — Liu et al. Erectile dysfunction and depression: a systematic review and meta-analysis
- PubMed — J Sex Med 2014 — Breyer et al. Sexual dysfunction in male Iraq and Afghanistan war veterans: association with PTSD
- PubMed — Behav Sci 2016 — Park et al. Is internet pornography causing sexual dysfunctions? A review with clinical reports
- PubMed — J Sex Med 2015 — Landripet & Štulhofer. Is pornography use associated with sexual difficulties and dysfunctions among younger heterosexual men?
- PubMed — J Sex Med 2019 — Grubbs & Gola. Is pornography use related to erectile functioning?
- PubMed — J Sex Med 2018 — Bossio et al. Mindfulness-based group therapy for men with situational erectile dysfunction


